Decided to stop posting in Madicine@ and Surgicomania.
Notice that there's not much of HO in East Malaysia who blogs.
Many medical students or potential ones may be curious about life as a HO in Sabah and Sarawak.
Starting another blog. Days of my life....
Thanks for the comments in the clinical cases that I've posted.
Didn't know that there's actually someone out there who knew the existence of this blog.
Friday, September 30, 2011

Monday, August 23, 2010
Briefly about Pancreatic Pseudocyst
Pancreatic pseudocyst is defined as single/multiple fluid collection with high amylase content, surrounded by fibrous or granulation tissue within the lesser sac.

It usually occurs around 4 weeks after an acute attack of pancreatitis, where patient complains of epigastric fullness, pain, nausea and vomiting.
If it's infected, there may be fever, rigors and sweating.
However, pseudocyst can be also caused by chronic pancreatitis or any pancreatic trauma.
Abdominal examination
Firm, tender epigastric mass is felt, with indistinct lower edge, and inability to get above the swelling.
It moves slightly with respiration.
Percussion reveals resonant note since the pseudocyst is covered by stomach.
However, it's not possible to demonstrate fluctuation and fluid thrill.
Investigations
Pancreatic pseudocyst must be differentiated from acute fluid collection and pancreatic abscess.
Usually just based on the clinical scenario and USG abdomen (or sometimes CT), one will be able to distinguish these conditions.
However, one must not forget that a cystic neoplasm may mimic as a chronic pseudocyst.
To differentiate, one needs to perform aspiration of the swelling under EUS guidance (EUS = endoscopic ultrasound).
Then, sent the aspirate for amylase level, cytology and CEA level.
Typically, if it's a chronic pseudocyst - high amylase level, with leucocytes and CEA < 400 ng/ml.
However, in case of mucinous neoplasm - CEA > 400 ng/ml.
Complications

Treatment
Treatment consist of drainage of the pseudocyst.
There are 3 approaches towards the drainage :
1) Percutaneous transgastric cystogastrostomy under imaging guidance, then by placing a double pigtail catheter, one end within the cystic cavity, another within the gastric lumen for drainage.
Chance of recurrence : not more than 15 %

2) Endoscopic method under EUS guidance : By puncturing the wall of stomach/duodenum to gain access into the pseudocyst cavity, then insertion of a drainage tube one end within the cystic cavity, another within the gastric lumen for drainage.
3) Surgical method by internal drainage into gastric/jejunal lumen. Rate of recurrence is not more than 5%.
Wednesday, July 21, 2010
Colonic diverticular disease
Introduction
Colonic diverticular disease is very common in developed nations, which is related to their diet containing low dietary fibers.
It is estimated that in developed countries, there are about 60% of the population aged > 70 years old are affected by diverticular disease. But this condition is rare before 35 years old.
Incidence is more common among females.

Though the entire colon may be affected, but the commonest site is the sigmoid colon, probably after intake of low residual diet, the intramural pressure over sigmoid colon is the highest.
Pulsion of diverticulae emerged in between the mesenteric and anti-mesenteric taenia, through the circular muscles, at points where the blood vessels penetrates through it.
Hence, diverticular disease will never occur in the rectum.
This is due to it's different arrangement of blood vessel, and it's longitudinal smooth muscle covers the entire circumference of the rectum.
Sometimes, a caecal diverticula may be obstructed by a faecolith or by inflammatory processes.
Hence resulting in acute appendicitis (mimics simple acute appendicitis)
Clinical features
Colonic diverticular disease are mostly asymptommatic.
Most of the cases are detected during investigation of other GI diseases, where diverticular disease are found incidentally.
Occasionally, patient may present with intermittent lower abdominal/LIF pain and tenderness.
Other symptoms include minor rectal bleeding, defecation urgency, altered bowel habits, etc.

Barium enema shows intestinal smooth muscular hypertrophy with multiple diverticula.
Complications
1) Perforation
Purulent peritonitis
Fecal peritonitis
2) Inflammation
Pericolic abscess

Peridiverticulitis
3) Fistula formation
Colovaginal
Colovesical
Colocolonic
Colocutaneous
4) Intestinal obstruction
Colonic fibrous fistula
Inflammatory mass, fistula
Adherent loops of small bowel
5) Bleeding
Chronic intermittent bleeding
Massive lower GI bleeding
Acute diverticulitis
1) History
Initially, patient may complains of intermittent lower abdominal pain.
Later, the pain is shifted to the left iliac fossa, which gradually becomes more constant, dull aching in nature.
If there's intestinal obstruction, the pain can be colicky in nature as well.
Often, there is lost of appetite, and nausea (rarely vomiting).
If the colonic vault is close to the bladder, it is not uncommon for the patient to have bladder symptoms (frequency, dysuria)
2) On examination
Patient appears in obvious distress, with fever and tachycardia.
Over the left iliac fossa, there is significant tenderness and guarding.
Occasionally, a tender, sausage-shaped mass may be palpable over the left iliac fossa.
Reverse Rovsing's sign is +ve : RIF is pressed, and pain is felt over LIF.
If there's intestinal obstruction or generalised peritonitis, abdomen is distended, with rebound tenderness, while on auscultation, bowel sounds is hyperactive (obstruction), or reduced (paralytic ileus - peritonitis).

Acute diverticulitis can be confirmed by Barium enema.
However, it is better to have it done 4-6 weeks later after infection has subsided.
Management
Nil by mouth
Bed rest
IV fluids
Antibiotics (Cephalosporins, Metronidazole)
If doesn't resolve, suspect pericolic abscess formation.
May requires incision and drainage of abscess, surgical resection, peritoneal toilet.
Friday, May 7, 2010
Acute Pancreatitis and CA pancreas
Introduction

Defined as activation of the pancreatic enzyme resulting in autolysis of the gland.
It is important to investigate for the possible causes of Acute pancreatitis before labeling it as 'idiopathic'.
Possible aetiology of Acute pancreatitis :
Gall stones
Alcoholism
Post ERCP
Abdominal trauma
Complication of cardiothoracic, biliary and abdominal surgery
Hypercalcemia
Hyperparathyroidism
Pancreatic Divisum
Autoimmune pancreatitis
Scorpion bite
Drugs : Corticosteroids, Azathioprine, Thiazide diuretics
Mumps, Cocksakie viral infection
Idiopathic
History
Both males and females are equally affected.
Age of onset is around 4th - 5th decade of life.
History of any gall stone diseases, or alcoholism is important (2 most important cause)
Though rare, but ask for recent contact with children with mumps or cocksakie infection.
Symptoms are usually triggered after consumption of large meal or alcohol.
Patient usually complains of sudden onset of severe, continuous epigastric pain, which typically radiates to the back, relieved by bending forwards.
It's accompanied by excessive vomiting and retching, with persistent nausea in between.
Breathing and movements exacerbates the pain.
General examination
Patient appears ill, with shallow breathing.
If the patient looks pale, diaphoretic, it is likely that it has complicated as a hypovolemic shock.
There might be mildly tinged jaundice if the pancreatitis is caused by gall stones.
Even 2-3 days after the illness, the mild tinged jaundice can be caused by compression of biliary duct by edematous head of pancreas.
Shock features of tachycardia, hypotension.
Low grade fever may or may not present.
Abdominal examination
In acute pancreatitis, the complains of the patient may indicate severe pain, but there is usually minimal findings
during abdominal examination.
 Cullen's sign
 Grey Turner's sign
On inspection, if there's haemorrhagic pancreatits, there might be bruising (bluish purplish) discolouration over around the umbilicus (Cullen's sign) or left flank (Grey Turner's sign).
However, these signs are rarely seen nowadays.
The abdomen may not rise and fall with respiration, since the musculature is tightly contracted, and during onset of paralytic ileus.
Often there is accumulation of inflammatory exudates within the lesser sac, which eventually forms pseudocyst, suggested by epigastric fullness (distension), dullness during percussion over it.
Shifting dullness may be present, bowel sound may be reduced if there is pancreatic ascites.
Invesitgations
Acute pancreatitis is usually diagnosed by typical clinical presentation and laboratory investigation that reveals elevated serum amylase level. Serum amylase of 3-4 times greater than the normal level is suggestive of pancreatitis.
However, if serum lipase assay is available, it is more sensitive and specific.
Note that normal serum amylase level doesn't rule out Acute pancreatitis, and the level poorly correlates with the severity.
Both Ranson's and Glasgow's criteria is used to grade the severity of Acute pancreatitis.
If 3 or more factors are present in the patient, it indicates severe pancreatitis.
 Imaging studies
Chest X ray, and plain abdominal X ray is not very helpful in the diagnosis of Acute pancreatitis
During early stages, if abdominal X ray is taken, non-specific signs such as Sentinel loop, Renal Halo sign or Colon cut off sign may be present.
 Sentinel loop
 Colon cut-off sign
Chest X ray may reveal pleural effusion, or if there is diffuse alveolar infiltrates, indicates ARDS.
Though Abdominal USG is non-diagnostic for Acute pancreatitis, but it must be done within 24 hours of presentation.
This is to rule out Acute cholecystitis as a differential diagnosis, to check whether the bile duct is dilated and to reveal any stones within the CBD (gall stone as a cause of Pancreatitis)
CT abdomen is not indicated in every patient.
Only when :
1) Diagnostic uncertainty
2) Severe pancreatitis
3) Clinical deterioration, with multi-organ failure, sepsis
4) Local complications occurs
Complications

Pancreatic pseudocyst
Management
a) Conservative
1) Gain IV access and rapid fluid resuscitation.
2) Give analgesics (usually IM pethidine is given)
3) Nil by mouth
4) Insertion of NG tube to relieve vomiting
5) Enteral feeding - nasojejunal tube (to maintain adequate nutrition)
6) Urinary catheterization is done
7) Monitor pulse, BP, urine output and CVP
8) Give antibiotics to prevent secondary infection
b) Endoscopic
If gall stone is strongly suspected as the cause of pancreatitis, the stones should be removed by basket (dormia) through endoscopic sphincterotomy.
If there is severe pancreatitis, or cholangitis occurs, both sphinterotomy and ERCP is done.
c) Surgery
Only indicated if : clinical deterioration during conservative management, unsure diagnosis, local complication occurs.
Adenocarcinoma of Pancreas
More common in males.
Age of presentation - 55-75 years old
85% of CA pancreas involves the head of pancreas, where the prognosis is usually poor.
Patients usually dies within 1 year of diagnosis (5 year survival is exceptional)
Upon presentation, most have progressed to a surgically incurable stage.
Though uncommon, but tumour arising from the distal CBD, duodenum and ampulla has a better outlook.
Currently, the risk factor of developing CA pancreas is thought to be :
Cigarette smoking
High fat and protein diet
Clinical features
Any elderly patient presents with painless jaundice, always suspect the possibility of Pancreatic cancer.
Typical symptoms are usually : Abdominal pain, jaundice and weight loss.
Jaundice is usually obstructive in nature, suggested by the classical triad of pruritus, clay-coloured stool and tea-coloured urine.
There might be steatorrhoea.
Abdominal pain - constant, dull aching, discomfort, over the epigastric region
Sought for symptoms of metastases
On examination, the gall bladder may be palpable, as accordance to the Curviosier's law, which states that,
"For patients presenting with clinically evident jaundice, and on examination the gall bladder is palpable, the cause is more likely to be due to Carcinoma of the Head of Pancreas".
Look for scleral icterus, hepatomegaly, etc.
Investigations
If stool occult blood test is positive, suggestive of a ampullary tumour.
Abdominal USG - usually done to look for liver metastases, or any mass lesion over the pancreas, and dilated bile ducts
CT abdomen - extent of metastases
To confirm the nature of obstruction, MRCP is preferred over ERCP since the former is less invasive.
Surgery of choice : Whipple's procedure


Defined as activation of the pancreatic enzyme resulting in autolysis of the gland.
It is important to investigate for the possible causes of Acute pancreatitis before labeling it as 'idiopathic'.
Possible aetiology of Acute pancreatitis :
Gall stones
Alcoholism
Post ERCP
Abdominal trauma
Complication of cardiothoracic, biliary and abdominal surgery
Hypercalcemia
Hyperparathyroidism
Pancreatic Divisum
Autoimmune pancreatitis
Scorpion bite
Drugs : Corticosteroids, Azathioprine, Thiazide diuretics
Mumps, Cocksakie viral infection
Idiopathic
History
Both males and females are equally affected.
Age of onset is around 4th - 5th decade of life.
History of any gall stone diseases, or alcoholism is important (2 most important cause)
Though rare, but ask for recent contact with children with mumps or cocksakie infection.
Symptoms are usually triggered after consumption of large meal or alcohol.
Patient usually complains of sudden onset of severe, continuous epigastric pain, which typically radiates to the back, relieved by bending forwards.
It's accompanied by excessive vomiting and retching, with persistent nausea in between.
Breathing and movements exacerbates the pain.
General examination
Patient appears ill, with shallow breathing.
If the patient looks pale, diaphoretic, it is likely that it has complicated as a hypovolemic shock.
There might be mildly tinged jaundice if the pancreatitis is caused by gall stones.
Even 2-3 days after the illness, the mild tinged jaundice can be caused by compression of biliary duct by edematous head of pancreas.
Shock features of tachycardia, hypotension.
Low grade fever may or may not present.
Abdominal examination
In acute pancreatitis, the complains of the patient may indicate severe pain, but there is usually minimal findings
during abdominal examination.
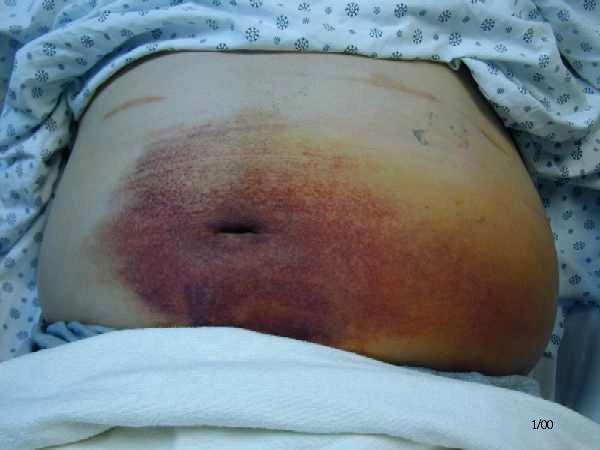

On inspection, if there's haemorrhagic pancreatits, there might be bruising (bluish purplish) discolouration over around the umbilicus (Cullen's sign) or left flank (Grey Turner's sign).
However, these signs are rarely seen nowadays.
The abdomen may not rise and fall with respiration, since the musculature is tightly contracted, and during onset of paralytic ileus.
Often there is accumulation of inflammatory exudates within the lesser sac, which eventually forms pseudocyst, suggested by epigastric fullness (distension), dullness during percussion over it.
Shifting dullness may be present, bowel sound may be reduced if there is pancreatic ascites.
Invesitgations
Acute pancreatitis is usually diagnosed by typical clinical presentation and laboratory investigation that reveals elevated serum amylase level. Serum amylase of 3-4 times greater than the normal level is suggestive of pancreatitis.
However, if serum lipase assay is available, it is more sensitive and specific.
Note that normal serum amylase level doesn't rule out Acute pancreatitis, and the level poorly correlates with the severity.
Both Ranson's and Glasgow's criteria is used to grade the severity of Acute pancreatitis.
If 3 or more factors are present in the patient, it indicates severe pancreatitis.

Chest X ray, and plain abdominal X ray is not very helpful in the diagnosis of Acute pancreatitis
During early stages, if abdominal X ray is taken, non-specific signs such as Sentinel loop, Renal Halo sign or Colon cut off sign may be present.


Chest X ray may reveal pleural effusion, or if there is diffuse alveolar infiltrates, indicates ARDS.
Though Abdominal USG is non-diagnostic for Acute pancreatitis, but it must be done within 24 hours of presentation.
This is to rule out Acute cholecystitis as a differential diagnosis, to check whether the bile duct is dilated and to reveal any stones within the CBD (gall stone as a cause of Pancreatitis)
CT abdomen is not indicated in every patient.
Only when :
1) Diagnostic uncertainty
2) Severe pancreatitis
3) Clinical deterioration, with multi-organ failure, sepsis
4) Local complications occurs
Complications

Management
a) Conservative
1) Gain IV access and rapid fluid resuscitation.
2) Give analgesics (usually IM pethidine is given)
3) Nil by mouth
4) Insertion of NG tube to relieve vomiting
5) Enteral feeding - nasojejunal tube (to maintain adequate nutrition)
6) Urinary catheterization is done
7) Monitor pulse, BP, urine output and CVP
8) Give antibiotics to prevent secondary infection
b) Endoscopic
If gall stone is strongly suspected as the cause of pancreatitis, the stones should be removed by basket (dormia) through endoscopic sphincterotomy.
If there is severe pancreatitis, or cholangitis occurs, both sphinterotomy and ERCP is done.
c) Surgery
Only indicated if : clinical deterioration during conservative management, unsure diagnosis, local complication occurs.
Adenocarcinoma of Pancreas
More common in males.
Age of presentation - 55-75 years old
85% of CA pancreas involves the head of pancreas, where the prognosis is usually poor.
Patients usually dies within 1 year of diagnosis (5 year survival is exceptional)
Upon presentation, most have progressed to a surgically incurable stage.
Though uncommon, but tumour arising from the distal CBD, duodenum and ampulla has a better outlook.
Currently, the risk factor of developing CA pancreas is thought to be :
Cigarette smoking
High fat and protein diet
Clinical features
Any elderly patient presents with painless jaundice, always suspect the possibility of Pancreatic cancer.
Typical symptoms are usually : Abdominal pain, jaundice and weight loss.
Jaundice is usually obstructive in nature, suggested by the classical triad of pruritus, clay-coloured stool and tea-coloured urine.
There might be steatorrhoea.
Abdominal pain - constant, dull aching, discomfort, over the epigastric region
Sought for symptoms of metastases
On examination, the gall bladder may be palpable, as accordance to the Curviosier's law, which states that,
"For patients presenting with clinically evident jaundice, and on examination the gall bladder is palpable, the cause is more likely to be due to Carcinoma of the Head of Pancreas".
Look for scleral icterus, hepatomegaly, etc.
Investigations
If stool occult blood test is positive, suggestive of a ampullary tumour.
Abdominal USG - usually done to look for liver metastases, or any mass lesion over the pancreas, and dilated bile ducts
CT abdomen - extent of metastases
To confirm the nature of obstruction, MRCP is preferred over ERCP since the former is less invasive.
Surgery of choice : Whipple's procedure

Thursday, May 6, 2010
Peptic ulcer disease and Gastric Carcinoma
Both duodenal ulcers and benign gastric ulcers are believed to be related to mucosal infection by H.pylori.
Peptic ulcer disease are mainly classified as complicated and uncomplicated.

Benign gastric ulcer/duodenal ulcer
Age of presentation ranges from 20-60 years old, which is of course, more common among young adults.
Incidence is higher in males.
Most patients during acute presentation will present with epigastric discomfort or pain.
The intensity ranges from mild dyspepsia (related to food intake, sensation of indigestion), to severe epigastric pain, which often forces the patient to lie down still.
However, as the course of illness goes chronic, pain is rarely severe.
A characteristic feature is night pain, which is a dull, boring ache often wakes patients from sleep.
This is due to the increased gastric acidity at night, and there is lack of food to buffer against it.
The pain either radiates to the back, or towards the RHC (depends on the position of the ulcer : posterior part of stomach, duodenum)
Patient may complain of heart burn, excessive salivation (water/acid brash) related to food intake.
In duodenal ulcer, food intake relieves the symptoms. Hence, patient rarely losses appetite.
In gastric ulcer, food intake aggravates the pain and often patient is apprehensive towards food.
Hence, history of appetite and weight loss is more common in them.
Vomiting relieves the pain in gastric ulcer.
The symptoms exhibit another characteristic, which is periodicity.
As the symptoms persisted for a few weeks, then it may be followed by a period of remission for weeks to months, only to recur after that.
Hemetemesis and malena must be asked in the history as well.
History of drug intake is important, eg : NSAIDs, steroids, salicylates
Other risk factors : Period of stress, cigarette smoking
Often, in examination, apart from abdominal tenderness (guarding if severe), and pallor if there's chronic silent bleeding, there is usually no other significant findings in examination.
Investigation
Full blood count and iron studies may reveals iron deficiency anemia.
Other blood investigations - hypokalemia, increased hematocrit as a result of vomiting.

The choice of imaging in peptic ulcer disease is oesophago-gastroduodenoscopy (OGDS).
Not only it allows visualization of the lesion, it allows mucosal specimens to be biopsied.
Usually biopsy is taken from the gastric antrum, and the specimen is subjected to CLO test.

CLO test consists of inoculating the specimen into a medium containing urea.
Hence, if the specimen contains H.pylori, which produces urease.
The enzyme reacts with urea, and produces ammonia, which changes the medium from yellow to pink/red colour.
That confirms the positive status of H.pylori in the patient.
Management
Due to the finding of Peptic ulcer disease is related to H.pylori infection, the management of uncomplicated peptic ulcer disease is mainly medical.
First of all, avoid smoking, alcohol, and NSAIDs.
However, if the patient requires long courses of NSAIDs, and his/her H.pylori status is -ve, a least damaging agent should be used, such as ibuprofen.
Anti-secretory agents such as proton pump inhibitors, H2 blockers are used.
To supplement these agents, drugs like sucralfate, bismuth compounds, prostaglandin analogues are used.
Eradication of H.pylori
Regardless whether it's a duodenal ulcer/gastric ulcer, once the patient is H.pylori positive, eradication regime of H.pylori is employed.
Usually consist of 1 proton pump inhibitor and 1 or more antibiotics.
In case of duodenal ulcer, if the patient is compliant to the medication, the success rate of remission is about 90%.
Without the eradication regime, the chances of relapse within 1 year is about 80%.
Any persistence of symptoms, a urea breath test (non-invasive) should be done to reassess the H.pylori status in the patient.
However, it must be done 4 weeks after completion of the eradication regime.
Or else, the therapy merely suppresses the bacteria, and may lead to a false negative test result.
However, in gastric ulcer, biopsy need to be taken before making a diagnosis of benign gastric ulcer.
Then if found benign, eradication therapy is given to all patients with +ve status of H.pylori.
Surveillance of the lesion need to be done until the ulcer heals.
Any persistence of symptoms, further biopsy must be taken.
Perforated peptic ulcer
Occasionally, the gastric juices erodes through the gastric/duodenal wall to the extent that only covering left is the visceral peritoneum. The gastric juices collects within the peritoneal cavity, leading to chemical peritonitis.
Eventually, there'll be secondary bacterial infection, leading to spontaneous bacterial peritonitis.
History
Age of presentation : Usually 40-60 years old
History of drug intake : NSAIDs, Steroids, Salicylates
Symptoms :
Sudden onset of severe, continuous abdominal pain which initially confines to the epigastrium.
It rapidly increases in it's intensity, and eventually the pain becomes generalized.
Breathing, movements aggravates the abdominal pain.
Also ask for previous peptic ulcer disease, or history of dyspepsia.
General Examination :
Patient usually lies still on bed, breaths shallowly, and is in a state of distress.
Temperature is usually normal, there might be tachycardia.
On abdominal examination :
On inspection, the abdomen doesn't rise and fall with respiration.
This is due to the tight contraction of the abdominal musculature.
On palpation, abdominal tenderness and guarding initially confines towards the epigastrium.
Later, if the peritonitis becomes generalized, the entire abdomen is tender, and there is intense guarding.
This results in the abdomen being described of having board-like rigidity.
It is impossible to palpate for the abdominal viscus since the muscles are tightly contracted.
On percussion, there may be obliteration/diminished liver dullness (due to the air escaped from the perforated viscus into the peritoneal cavity.
Shifting dullness may be +ve.
On auscultation, bowel sound may be reduced, which indicates generalised peritonitis.
Note : 4-6 hours later, due to the dilution of the accumulated gastric juices within the peritoneal cavity, the patient's symptoms and signs subsides, and the patient actually thought that his/her condition is improving. This is mainly due to the onset of hypovolemic shock, which may be indicated by the presence of increasing abdominal distension, tachycardia, signs of dehydration and etc.
Investigation

In 60% of the patients, the CXR reveals air-filled under the diagphram.
However, absent of this finding does not exclude perforation.
Lateral Chest X-ray may be useful in case an erect CXR is not feasible (patient may be in the state of shock, disability)
In laboratory investigation, there is usually some degree of elevated serum amylase level.
However, 3-4 folds elevated serum amylase level is more suggestive of pancreatitis.
Management
1) Give fluid resuscitation
2) Analgesic for relief of pain
3) IV unasyn and flagyl
4) Anti-emetics are given
5) Insertion of NG tube, and catheterize the patient (monitoring of urine output)
Only after the patient is stable, surgical intervention is done.
In case of a perforated duodenal ulcer, usually simple closure is performed by using an omental patch.

However, if it's a perforated gastric ulcer, a biopsy need to be taken first (to rule out malignancy)
Then, close the perforation by either simple closure or local excision.
During post-op period, IV gastric anti-secretory agent is given.
Pyloric stenosis
First of all, lets take a look at some causes of gastric outlet obstruction :
Peptic ulcer disease
Malignancy (Stomach, pancreas and lymphoma)
Crohn's disease of duodenum
Inflammation of surrounding structures
Gastroparesis (autonomic neuropathy)
Adult hypertrophic pyloric stenosis
 Patients with long standing peptic ulcer disease may develop pyloric stenosis due to healing of the ulcer via fibrosis at the level of the antrum.
Usually, the complaints are :
Early satiety
Sensation of fullness, constant epigastric discomfort/pain
History of weight loss
Projectile vomiting is classical, which consists of non-bilious, undigested food particles.
It usually occurs when the patient is lying down, and following the vomiting, it relieves the sensation of fullness.
On examination, the usual findings includes :
On inspection - epigastric distension, visible peristalsis
On palpation - succussion splash ('splashing' sound heard while the abdomen is shaked right-left-right)
Investigation of choice is by OGDS, to determine the nature of obstruction (notice that the symptoms mimics malignancy)
Note that not all patients requires surgical intervention.
A course of PPI can be given first, in hope that when the ulcer heals, the stenosis is resolved.
However, if not reponsive, surgical options includes :

Pyloroplasty or Gastrojejunostomy
Gastric carcinoma
One of the most common cause of death in men.
Pernicious anemia, gastric polyps and chronic gastric ulcers are known pre-malignant conditions.
 Risk factors :
1) Diet
High intake of salt, nitrosamines (usually present in preservatives)
Gastric CA is more prevalent in countries which malnutrition is a problem.
High intake of vitamin C and E seems to be protective.
2) History of surgery : Gastroenterostomy
3) Type A blood group
4) Atrophic gastritis secondary to Pernicious anemia
5) Chronic gastric ulcer
6) Gastric polyps
History
Age of onset : around 50-70 years of age
Male predominance
Any individual above 45 years of age, presenting with symptoms of dyspepsia, no matter how vague is it, should be investigated.
The epigastric discomfort may not be always associated with food intake.
Patient with long standing history of peptic ulcer disease may notice the change in the character of pain.
Usually it's the periodicity of pain becoming more constant.
There's usually complains of early satiety as well.
Another prominent symptom of Gastric CA is significant loss in appetite, which results in loss of weight.
Patient can lose around 10-20 kg of weight within 1-2 months.
If the tumour is present at the region of gastric cardia, patient may report of progressively worsening dysphagia, and eventually it may be worse enough to cause regurgitation of food contents.
If the tumour is present over the gastric outlet, there may be symptoms of gastric outlet obstruction.
Next is to sought the history of the risk factors mentioned above.
And please elicit history suggestive of metastases to the lung, liver, bones, and brain.
Examination
On general examination, the significant findings includes pallor, cachexia and probably jaundice.
Severe wasting is most noticeable over the hands and face.
Presence of jaundice (usually scleral icterus) indicates liver metastases.
Please look for evidence of an enlarged Virchow's node (left supraclavicular node)
On abdominal examination :
Inspection : abdomen is usually scaphoid, due to the severe wasting. Paradoxically, the abdomen may be distended due to malignant ascites.
Palpation : usually reveals deep tenderness over the epigastric region. In thin patients, deep palpation on full inspiration sometimes reveals a hard, irregular mass. Liver may be palpable, which is hard in consistency, knobbly in surface, non-tender.
Percussion : shifting dullness is +ve if there is malignant ascites
On systemic examination : evidence of metastases (pleural effusion, bony tenderness)
Peptic ulcer disease are mainly classified as complicated and uncomplicated.

Benign gastric ulcer/duodenal ulcer
Age of presentation ranges from 20-60 years old, which is of course, more common among young adults.
Incidence is higher in males.
Most patients during acute presentation will present with epigastric discomfort or pain.
The intensity ranges from mild dyspepsia (related to food intake, sensation of indigestion), to severe epigastric pain, which often forces the patient to lie down still.
However, as the course of illness goes chronic, pain is rarely severe.
A characteristic feature is night pain, which is a dull, boring ache often wakes patients from sleep.
This is due to the increased gastric acidity at night, and there is lack of food to buffer against it.
The pain either radiates to the back, or towards the RHC (depends on the position of the ulcer : posterior part of stomach, duodenum)
Patient may complain of heart burn, excessive salivation (water/acid brash) related to food intake.
In duodenal ulcer, food intake relieves the symptoms. Hence, patient rarely losses appetite.
In gastric ulcer, food intake aggravates the pain and often patient is apprehensive towards food.
Hence, history of appetite and weight loss is more common in them.
Vomiting relieves the pain in gastric ulcer.
The symptoms exhibit another characteristic, which is periodicity.
As the symptoms persisted for a few weeks, then it may be followed by a period of remission for weeks to months, only to recur after that.
Hemetemesis and malena must be asked in the history as well.
History of drug intake is important, eg : NSAIDs, steroids, salicylates
Other risk factors : Period of stress, cigarette smoking
Often, in examination, apart from abdominal tenderness (guarding if severe), and pallor if there's chronic silent bleeding, there is usually no other significant findings in examination.
Investigation
Full blood count and iron studies may reveals iron deficiency anemia.
Other blood investigations - hypokalemia, increased hematocrit as a result of vomiting.

The choice of imaging in peptic ulcer disease is oesophago-gastroduodenoscopy (OGDS).
Not only it allows visualization of the lesion, it allows mucosal specimens to be biopsied.
Usually biopsy is taken from the gastric antrum, and the specimen is subjected to CLO test.

CLO test consists of inoculating the specimen into a medium containing urea.
Hence, if the specimen contains H.pylori, which produces urease.
The enzyme reacts with urea, and produces ammonia, which changes the medium from yellow to pink/red colour.
That confirms the positive status of H.pylori in the patient.
Management
Due to the finding of Peptic ulcer disease is related to H.pylori infection, the management of uncomplicated peptic ulcer disease is mainly medical.
First of all, avoid smoking, alcohol, and NSAIDs.
However, if the patient requires long courses of NSAIDs, and his/her H.pylori status is -ve, a least damaging agent should be used, such as ibuprofen.
Anti-secretory agents such as proton pump inhibitors, H2 blockers are used.
To supplement these agents, drugs like sucralfate, bismuth compounds, prostaglandin analogues are used.
Eradication of H.pylori
Regardless whether it's a duodenal ulcer/gastric ulcer, once the patient is H.pylori positive, eradication regime of H.pylori is employed.
Usually consist of 1 proton pump inhibitor and 1 or more antibiotics.
In case of duodenal ulcer, if the patient is compliant to the medication, the success rate of remission is about 90%.
Without the eradication regime, the chances of relapse within 1 year is about 80%.
Any persistence of symptoms, a urea breath test (non-invasive) should be done to reassess the H.pylori status in the patient.
However, it must be done 4 weeks after completion of the eradication regime.
Or else, the therapy merely suppresses the bacteria, and may lead to a false negative test result.
However, in gastric ulcer, biopsy need to be taken before making a diagnosis of benign gastric ulcer.
Then if found benign, eradication therapy is given to all patients with +ve status of H.pylori.
Surveillance of the lesion need to be done until the ulcer heals.
Any persistence of symptoms, further biopsy must be taken.
Perforated peptic ulcer
Occasionally, the gastric juices erodes through the gastric/duodenal wall to the extent that only covering left is the visceral peritoneum. The gastric juices collects within the peritoneal cavity, leading to chemical peritonitis.
Eventually, there'll be secondary bacterial infection, leading to spontaneous bacterial peritonitis.
History
Age of presentation : Usually 40-60 years old
History of drug intake : NSAIDs, Steroids, Salicylates
Symptoms :
Sudden onset of severe, continuous abdominal pain which initially confines to the epigastrium.
It rapidly increases in it's intensity, and eventually the pain becomes generalized.
Breathing, movements aggravates the abdominal pain.
Also ask for previous peptic ulcer disease, or history of dyspepsia.
General Examination :
Patient usually lies still on bed, breaths shallowly, and is in a state of distress.
Temperature is usually normal, there might be tachycardia.
On abdominal examination :
On inspection, the abdomen doesn't rise and fall with respiration.
This is due to the tight contraction of the abdominal musculature.
On palpation, abdominal tenderness and guarding initially confines towards the epigastrium.
Later, if the peritonitis becomes generalized, the entire abdomen is tender, and there is intense guarding.
This results in the abdomen being described of having board-like rigidity.
It is impossible to palpate for the abdominal viscus since the muscles are tightly contracted.
On percussion, there may be obliteration/diminished liver dullness (due to the air escaped from the perforated viscus into the peritoneal cavity.
Shifting dullness may be +ve.
On auscultation, bowel sound may be reduced, which indicates generalised peritonitis.
Note : 4-6 hours later, due to the dilution of the accumulated gastric juices within the peritoneal cavity, the patient's symptoms and signs subsides, and the patient actually thought that his/her condition is improving. This is mainly due to the onset of hypovolemic shock, which may be indicated by the presence of increasing abdominal distension, tachycardia, signs of dehydration and etc.
Investigation

In 60% of the patients, the CXR reveals air-filled under the diagphram.
However, absent of this finding does not exclude perforation.
Lateral Chest X-ray may be useful in case an erect CXR is not feasible (patient may be in the state of shock, disability)
In laboratory investigation, there is usually some degree of elevated serum amylase level.
However, 3-4 folds elevated serum amylase level is more suggestive of pancreatitis.
Management
1) Give fluid resuscitation
2) Analgesic for relief of pain
3) IV unasyn and flagyl
4) Anti-emetics are given
5) Insertion of NG tube, and catheterize the patient (monitoring of urine output)
Only after the patient is stable, surgical intervention is done.
In case of a perforated duodenal ulcer, usually simple closure is performed by using an omental patch.
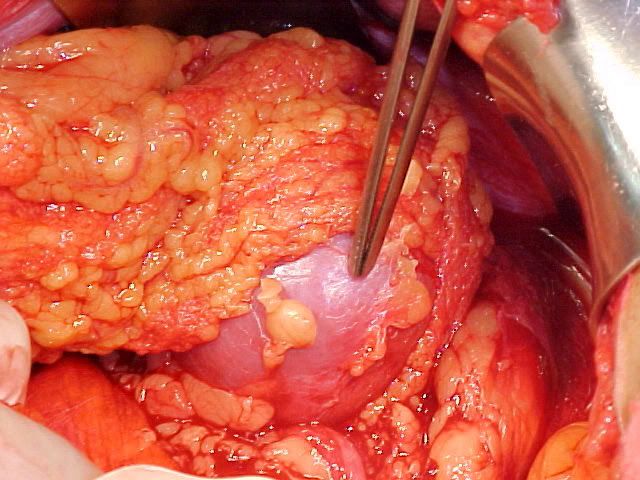
However, if it's a perforated gastric ulcer, a biopsy need to be taken first (to rule out malignancy)
Then, close the perforation by either simple closure or local excision.
During post-op period, IV gastric anti-secretory agent is given.
Pyloric stenosis
First of all, lets take a look at some causes of gastric outlet obstruction :
Peptic ulcer disease
Malignancy (Stomach, pancreas and lymphoma)
Crohn's disease of duodenum
Inflammation of surrounding structures
Gastroparesis (autonomic neuropathy)
Adult hypertrophic pyloric stenosis

Usually, the complaints are :
Early satiety
Sensation of fullness, constant epigastric discomfort/pain
History of weight loss
Projectile vomiting is classical, which consists of non-bilious, undigested food particles.
It usually occurs when the patient is lying down, and following the vomiting, it relieves the sensation of fullness.
On examination, the usual findings includes :
On inspection - epigastric distension, visible peristalsis
On palpation - succussion splash ('splashing' sound heard while the abdomen is shaked right-left-right)
Investigation of choice is by OGDS, to determine the nature of obstruction (notice that the symptoms mimics malignancy)
Note that not all patients requires surgical intervention.
A course of PPI can be given first, in hope that when the ulcer heals, the stenosis is resolved.
However, if not reponsive, surgical options includes :

Pyloroplasty or Gastrojejunostomy
Gastric carcinoma
One of the most common cause of death in men.
Pernicious anemia, gastric polyps and chronic gastric ulcers are known pre-malignant conditions.

1) Diet
High intake of salt, nitrosamines (usually present in preservatives)
Gastric CA is more prevalent in countries which malnutrition is a problem.
High intake of vitamin C and E seems to be protective.
2) History of surgery : Gastroenterostomy
3) Type A blood group
4) Atrophic gastritis secondary to Pernicious anemia
5) Chronic gastric ulcer
6) Gastric polyps
History
Age of onset : around 50-70 years of age
Male predominance
Any individual above 45 years of age, presenting with symptoms of dyspepsia, no matter how vague is it, should be investigated.
The epigastric discomfort may not be always associated with food intake.
Patient with long standing history of peptic ulcer disease may notice the change in the character of pain.
Usually it's the periodicity of pain becoming more constant.
There's usually complains of early satiety as well.
Another prominent symptom of Gastric CA is significant loss in appetite, which results in loss of weight.
Patient can lose around 10-20 kg of weight within 1-2 months.
If the tumour is present at the region of gastric cardia, patient may report of progressively worsening dysphagia, and eventually it may be worse enough to cause regurgitation of food contents.
If the tumour is present over the gastric outlet, there may be symptoms of gastric outlet obstruction.
Next is to sought the history of the risk factors mentioned above.
And please elicit history suggestive of metastases to the lung, liver, bones, and brain.
Examination
On general examination, the significant findings includes pallor, cachexia and probably jaundice.
Severe wasting is most noticeable over the hands and face.
Presence of jaundice (usually scleral icterus) indicates liver metastases.
Please look for evidence of an enlarged Virchow's node (left supraclavicular node)
On abdominal examination :
Inspection : abdomen is usually scaphoid, due to the severe wasting. Paradoxically, the abdomen may be distended due to malignant ascites.
Palpation : usually reveals deep tenderness over the epigastric region. In thin patients, deep palpation on full inspiration sometimes reveals a hard, irregular mass. Liver may be palpable, which is hard in consistency, knobbly in surface, non-tender.
Percussion : shifting dullness is +ve if there is malignant ascites
On systemic examination : evidence of metastases (pleural effusion, bony tenderness)
Wednesday, May 5, 2010
Gall Stones
Pathophysiology

Mostly cholesterol stones (80%), pigment stones or mixed stones.
Whether cholesterol remains as solution within bile depends on it's concentration, and the levels of phospholipids and bile acids within.
If the bile is supersaturated by cholesterol, and/or levels of phospholipids and bile acids is low, this promotes formation of cholesterol crystals.
These cholesterol crystals are toxic towards the gall bladder musculature, and hence damages it.
This results in gall bladder hypomotility, and enhances the nucleation of theses gall bladder crystals.
Eventually, gall stones are formed.
As for pigment stones, there are 2 types, namely black and brown stones.
Black stones are sterile stones, usually caused by extensive hemolysis leading to unconjugated hyperbilirubinemia. Eg, seen in Hereditary Spherocytosis, Sickle-cell disease.
Whilst brown stones are non-sterile stones, mainly caused by infection.
Eg, certain bacteria (E.coli) produces B-glucoronidase, which converts conjugated bilirubin back to unconjugated bilirubin.
Also associated with parasitic worm infestation, eg : Ascariasis, Clonorchis sinensis
Complications

1) Gall bladder
Biliary colic
Acute cholecystitis
Chronic cholecystitis
Empyema
Mucocele
Perforation
2) Biliary tract
Biliary tract obstruction
Acute pancreatitis
Ascending cholangitis
3) Intestine
Gall stone ileus
Acute cholecystitis
Usually caused by obstruction of cystic duct by gall stones, leading to gall bladder distension, chemical inflammation, and eventual bacterial infection.
History
Age : Typically 30-60 years old. Presentation in younger patients, may be due to Congenital hemolytic anemia
Gender : Females are more commonly affected
Symptoms :
Fever
Sudden onset of severe, continuous RHC pain
Radiates to the back (close to the inferior angle of right scapula)
Associated with nausea and vomiting
Duration of pain usually exceeds 3-6 hours
Pain aggravated by movements and breathing
May have previous h/o of flatulent dyspepsia or biliary colic
On general examination :
Patient appears ill
Lying still on bed, breathing shallowly
Tachycardia +ve, Pyrexia +ve
During initial stages of inflammation - RHC fullness (known as Zackary-cope's sign)
RHC tenderness, guarding/rigidity, +ve Murphy's sign
Before the onset of guarding, during the early stages the gall bladder may be palpable
If the inflammation persisted for a few days, with subsequent subside of symptoms, an inflammatory mass may be palpable (empyema)
Boas Sign +ve
Biliary colic
Before proceeding to investigations of Acute cholecystitis, briefly about biliary colic.
It's actually a misnomer, caused by spasm of gall bladder musculature, trying to force the stone down the cystic duct.
Since it's a visceral pain, pain is usually felt over the epigastrium (foregut)
The pain is typically aggravated by intake of oily food.
Since after ingesting oily food, as it passes through the 2nd part of duodenum, it stimulates the production of cholecystikinin from the duodenal mucosa.
It causes contraction of the gall bladder musculature over the stones, hence causing pain.
Duration of pain typically lasted < 3 hours.
However, in practice, patient usually localizes their pain poorly (c/c usually diffuse upper abdominal pain)
It's a pseudocolic, since there's no complete relief of pain in between periods of excruciating exacerbations.
There might be nausea and vomiting.
On examination, there may be tachycardia, but fever is absent.
On abdominal examination, other than tenderness, guarding, usually there's no other signs.
Hence, there's a frequent overlap in between the clinical features of biliary colic and acute cholecystitis.
Here the table showing their difference :
 Investigations
Full blood count - reveals leucocytosis
Abdominal X ray - not useful, only 10-15% of the calculus is visible through plain abdominal X ray
USG abdomen - visualisation of gall bladder wall, contents, biliary tree
Management
As for asymptommatic gall stones, which is usually detected incidentally, the best option is to observe (no further intervention)
However, prophylactic cholecystectomy will be indicated in :
a) Non-functioning gall bladder
b) Gall bladder with calcified/thickened wall
c) Diabetic patients (prevent Emphysematous Cholecystitis)
d) Multiple small stones (risk of stones rolling into CBD)
e) Congenital hemolytic anemia
During acute presentation, > 90% of the cases, symptoms subsides with conservative management :
1) Nil by mouth
2) Administration of analgesics
3) Administration of antibiotics (Unasyn + Flagyl)
4) Gain IV access, give IV fluids
5) Monitoring of vital signs
6) If symptoms subsided, initially oral fluid intake is allowed, then followed by fat-free diet, and lastly regular diet
7) USG - to evaluate whether there's any local complications
8) Plan for cholecystectomy
Pre-operative investigations
1) Informed consent
2) Full blood count
3) BUSE/Creatinine
4) Liver function test
5) ECG, Chest X ray (if medically indicated)
6) Antibiotic prophylaxis
7) DVT prophylaxis
Cholecystectomy can be done via laproscopic approach or laparotomy.
Gall stone ileus
Small bowel obstruction caused by gall stone impaction at the distal ileum
Usually seen in females, age > 60 years old, with h/o of recurrent cholecystitis
Erosion of the stones through the duodenum, eventually forming a fistula with the distal ileum
Presentation is similar to any other small bowel obstruction
Plain abdominal X ray reveals multiple air-fluid levels, and there might be aerobilia (gas within biliary tree)
 Soft stones can be crushed
Hard stones requires enterotomy
Mirizzi's syndrome
 A complication of cholecystitis
Gall stone impaction occurs at cystic duct.
There's impingement of the gall stone over the common hepatic duct, which eventually results in formation of a fistula in between the gall bladder and the bile duct.
An exception towards the Curvoisier's law.
Complications : Post-cholecystectomy
1) Haemorrhage
Usually the source is from cystic artery.
One should suspect possibility of haemorrhage if the patient complains of persistent abdominal pain, or features of hypovolemic shock during post-operative period
2) Infection
Drastically reduced after administration of prophylactic antibiotics before cholecystectomy.
3) Leakage of bile
Usually due to disrupted ligature, or accidental removal of any accessory ducts.
Patient usually complains of persistent abdominal pain.
If there's no biliary ascites -> ERCP
If there's biliary ascites -> Laparotomy
4) Post-cholecystectomy syndrome
5) Biliary stricture
6) Retained stone
Usually found during T-tube cholangiogram
Any procedure done to explore the common bile duct requires insertion of T-tube.
This is to prevent biliary stasis due to formation of stricture.
The opening of bile duct is sutured to the T-tube, which the long limb is brought out through an abdominal stab incision.
Any bile is collected through a bag.
7-10 days later, T-tube cholangiogram is done (iodine as contrast material)
If there's free flow of contrast material into the duodenum, and there's no residual stone -> remove the T-tube
If there's residual stone :
Stone is small - try using normal saline to irrigate the duct via the T tube (stone eventually migrates to the duodenum)
Stone is large - delayed removal after 4-6 weeks, via radiographically guided removal using dormia basket
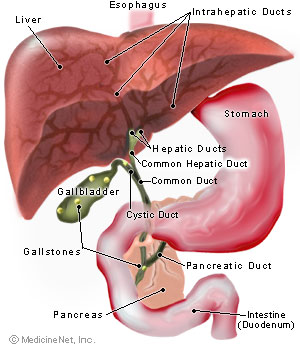
Mostly cholesterol stones (80%), pigment stones or mixed stones.
Whether cholesterol remains as solution within bile depends on it's concentration, and the levels of phospholipids and bile acids within.
If the bile is supersaturated by cholesterol, and/or levels of phospholipids and bile acids is low, this promotes formation of cholesterol crystals.
These cholesterol crystals are toxic towards the gall bladder musculature, and hence damages it.
This results in gall bladder hypomotility, and enhances the nucleation of theses gall bladder crystals.
Eventually, gall stones are formed.
As for pigment stones, there are 2 types, namely black and brown stones.
Black stones are sterile stones, usually caused by extensive hemolysis leading to unconjugated hyperbilirubinemia. Eg, seen in Hereditary Spherocytosis, Sickle-cell disease.
Whilst brown stones are non-sterile stones, mainly caused by infection.
Eg, certain bacteria (E.coli) produces B-glucoronidase, which converts conjugated bilirubin back to unconjugated bilirubin.
Also associated with parasitic worm infestation, eg : Ascariasis, Clonorchis sinensis
Complications
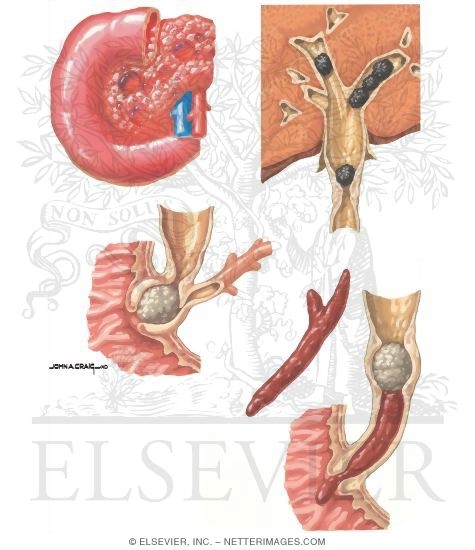
1) Gall bladder
Biliary colic
Acute cholecystitis
Chronic cholecystitis
Empyema
Mucocele
Perforation
2) Biliary tract
Biliary tract obstruction
Acute pancreatitis
Ascending cholangitis
3) Intestine
Gall stone ileus
Acute cholecystitis
Usually caused by obstruction of cystic duct by gall stones, leading to gall bladder distension, chemical inflammation, and eventual bacterial infection.
History
Age : Typically 30-60 years old. Presentation in younger patients, may be due to Congenital hemolytic anemia
Gender : Females are more commonly affected
Symptoms :
Fever
Sudden onset of severe, continuous RHC pain
Radiates to the back (close to the inferior angle of right scapula)
Associated with nausea and vomiting
Duration of pain usually exceeds 3-6 hours
Pain aggravated by movements and breathing
May have previous h/o of flatulent dyspepsia or biliary colic
On general examination :
Patient appears ill
Lying still on bed, breathing shallowly
Tachycardia +ve, Pyrexia +ve
During initial stages of inflammation - RHC fullness (known as Zackary-cope's sign)
RHC tenderness, guarding/rigidity, +ve Murphy's sign
Before the onset of guarding, during the early stages the gall bladder may be palpable
If the inflammation persisted for a few days, with subsequent subside of symptoms, an inflammatory mass may be palpable (empyema)
Boas Sign +ve
Biliary colic
Before proceeding to investigations of Acute cholecystitis, briefly about biliary colic.
It's actually a misnomer, caused by spasm of gall bladder musculature, trying to force the stone down the cystic duct.
Since it's a visceral pain, pain is usually felt over the epigastrium (foregut)
The pain is typically aggravated by intake of oily food.
Since after ingesting oily food, as it passes through the 2nd part of duodenum, it stimulates the production of cholecystikinin from the duodenal mucosa.
It causes contraction of the gall bladder musculature over the stones, hence causing pain.
Duration of pain typically lasted < 3 hours.
However, in practice, patient usually localizes their pain poorly (c/c usually diffuse upper abdominal pain)
It's a pseudocolic, since there's no complete relief of pain in between periods of excruciating exacerbations.
There might be nausea and vomiting.
On examination, there may be tachycardia, but fever is absent.
On abdominal examination, other than tenderness, guarding, usually there's no other signs.
Hence, there's a frequent overlap in between the clinical features of biliary colic and acute cholecystitis.
Here the table showing their difference :

Full blood count - reveals leucocytosis
Abdominal X ray - not useful, only 10-15% of the calculus is visible through plain abdominal X ray
USG abdomen - visualisation of gall bladder wall, contents, biliary tree
Management
As for asymptommatic gall stones, which is usually detected incidentally, the best option is to observe (no further intervention)
However, prophylactic cholecystectomy will be indicated in :
a) Non-functioning gall bladder
b) Gall bladder with calcified/thickened wall
c) Diabetic patients (prevent Emphysematous Cholecystitis)
d) Multiple small stones (risk of stones rolling into CBD)
e) Congenital hemolytic anemia
During acute presentation, > 90% of the cases, symptoms subsides with conservative management :
1) Nil by mouth
2) Administration of analgesics
3) Administration of antibiotics (Unasyn + Flagyl)
4) Gain IV access, give IV fluids
5) Monitoring of vital signs
6) If symptoms subsided, initially oral fluid intake is allowed, then followed by fat-free diet, and lastly regular diet
7) USG - to evaluate whether there's any local complications
8) Plan for cholecystectomy
Pre-operative investigations
1) Informed consent
2) Full blood count
3) BUSE/Creatinine
4) Liver function test
5) ECG, Chest X ray (if medically indicated)
6) Antibiotic prophylaxis
7) DVT prophylaxis
Cholecystectomy can be done via laproscopic approach or laparotomy.
Gall stone ileus
Small bowel obstruction caused by gall stone impaction at the distal ileum
Usually seen in females, age > 60 years old, with h/o of recurrent cholecystitis
Erosion of the stones through the duodenum, eventually forming a fistula with the distal ileum
Presentation is similar to any other small bowel obstruction
Plain abdominal X ray reveals multiple air-fluid levels, and there might be aerobilia (gas within biliary tree)

Hard stones requires enterotomy
Mirizzi's syndrome

Gall stone impaction occurs at cystic duct.
There's impingement of the gall stone over the common hepatic duct, which eventually results in formation of a fistula in between the gall bladder and the bile duct.
An exception towards the Curvoisier's law.
Complications : Post-cholecystectomy
1) Haemorrhage
Usually the source is from cystic artery.
One should suspect possibility of haemorrhage if the patient complains of persistent abdominal pain, or features of hypovolemic shock during post-operative period
2) Infection
Drastically reduced after administration of prophylactic antibiotics before cholecystectomy.
3) Leakage of bile
Usually due to disrupted ligature, or accidental removal of any accessory ducts.
Patient usually complains of persistent abdominal pain.
If there's no biliary ascites -> ERCP
If there's biliary ascites -> Laparotomy
4) Post-cholecystectomy syndrome
5) Biliary stricture
6) Retained stone
Usually found during T-tube cholangiogram
Any procedure done to explore the common bile duct requires insertion of T-tube.
This is to prevent biliary stasis due to formation of stricture.
The opening of bile duct is sutured to the T-tube, which the long limb is brought out through an abdominal stab incision.
Any bile is collected through a bag.
7-10 days later, T-tube cholangiogram is done (iodine as contrast material)
If there's free flow of contrast material into the duodenum, and there's no residual stone -> remove the T-tube
If there's residual stone :
Stone is small - try using normal saline to irrigate the duct via the T tube (stone eventually migrates to the duodenum)
Stone is large - delayed removal after 4-6 weeks, via radiographically guided removal using dormia basket
Tuesday, January 5, 2010
Intercostal drainage
Indications for intercostal drain :
a) Pneumothorax
b) Traumatic haemopneumothorax
c) Malignant pleural effusion
d) Empyema thoracis / Complicated parapneumonic effusion
e) Post-operative drainage : esophagectomy, cardiac surgery, thoracotomy
Equipments :
Intercostal tube or Chest tube (Size for pneumothorax : 36-40 Fr, hemothorax : 22-24 Fr)

Connecting tubes and compatible connectors
Underwater seal drainage bottle containing water upto mark

Line clamp
11 blade scalpel
Instruments for blunt dissection
Blue and Green needle
2 or 3/0 silk in a large hand-held needle
10ml syringe
20ml of 1% lidocaine
Normal saline
Sterile gloves
Sterile drapes
Sterile gauze
Skin prep. solution

Procedures :

1) Explain procedure to the patient if appropriate.
2) Connect the patient to a pulse oxymeter.
3) Prop up the patient to a semi-recumbent position, with the ipsilateral limb abducted.
4) Prepare the skin at the site of tube insertion (antiseptics)
5) Make proper drapping over field of interest.
6) Infiltrate the local anesthetic sufficiently, including the parietal pleura and the periosteum of the rib posterior to the line of incision.
7) Make a transverse, 2cm incison over the 5th intercostal space, over the mid-axillary line (may extend upto the anterior axillary line)
8) Proceed with blunt dissection until the pleura is visible.
9) Now, gently and firmly, by using a blunt-ended clamp, puncture the pleura, and widened the hole created.
10) Place one of your finger into the hole to ensure there's no adhesions.
11) Insert the chest tube without trochar into the puncture hole created after clamping it. Guide the tube superiorly if it's a pneumothorax, and towards the base if it's a hemothorax.
12) Fix the chest tube using the silk sutures.
13) Connect the distal end of the tube to the underwater seal drainage bottle, and remove the clamp.
Potential complications :
1) Misplacement (intra-parenchymal or subcutaneous)
2) Damaging the surrounding structures : liver, spleen, lungs, heart, aorta, diagphram, etc
3) Surgical emphysema
4) Wound infection, empyema
5) Pain
a) Pneumothorax
b) Traumatic haemopneumothorax
c) Malignant pleural effusion
d) Empyema thoracis / Complicated parapneumonic effusion
e) Post-operative drainage : esophagectomy, cardiac surgery, thoracotomy
Equipments :
Intercostal tube or Chest tube (Size for pneumothorax : 36-40 Fr, hemothorax : 22-24 Fr)

Connecting tubes and compatible connectors
Underwater seal drainage bottle containing water upto mark

11 blade scalpel
Instruments for blunt dissection
Blue and Green needle
2 or 3/0 silk in a large hand-held needle
10ml syringe
20ml of 1% lidocaine
Normal saline
Sterile gloves
Sterile drapes
Sterile gauze
Skin prep. solution

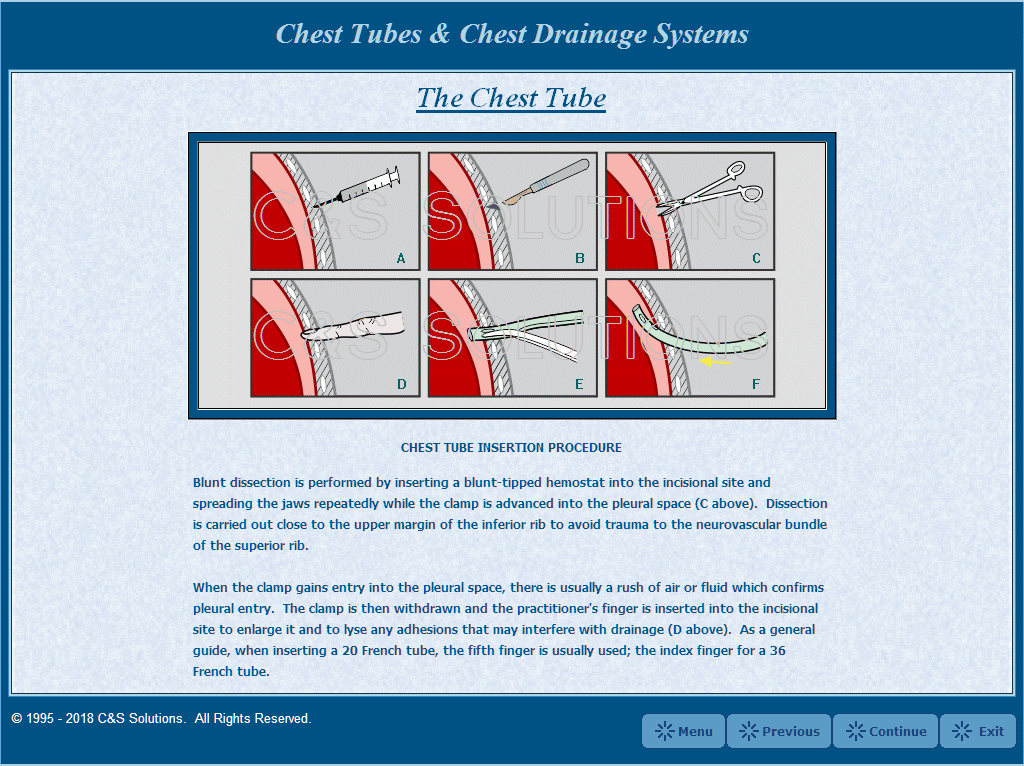
1) Explain procedure to the patient if appropriate.
2) Connect the patient to a pulse oxymeter.
3) Prop up the patient to a semi-recumbent position, with the ipsilateral limb abducted.
4) Prepare the skin at the site of tube insertion (antiseptics)
5) Make proper drapping over field of interest.
6) Infiltrate the local anesthetic sufficiently, including the parietal pleura and the periosteum of the rib posterior to the line of incision.
7) Make a transverse, 2cm incison over the 5th intercostal space, over the mid-axillary line (may extend upto the anterior axillary line)
8) Proceed with blunt dissection until the pleura is visible.
9) Now, gently and firmly, by using a blunt-ended clamp, puncture the pleura, and widened the hole created.
10) Place one of your finger into the hole to ensure there's no adhesions.
11) Insert the chest tube without trochar into the puncture hole created after clamping it. Guide the tube superiorly if it's a pneumothorax, and towards the base if it's a hemothorax.
12) Fix the chest tube using the silk sutures.
13) Connect the distal end of the tube to the underwater seal drainage bottle, and remove the clamp.
Potential complications :
1) Misplacement (intra-parenchymal or subcutaneous)
2) Damaging the surrounding structures : liver, spleen, lungs, heart, aorta, diagphram, etc
3) Surgical emphysema
4) Wound infection, empyema
5) Pain
Wednesday, December 30, 2009
Breast Lump
Anatomy of Breast
The vertical extent of breast is from 2nd-6th ribs inclusive.
The horizontal extent is from the lateral edge of sternum to the mid-axillary line.
2/3rds of the breast overlies the pectoralis major muscle, whereas 1/3 of it over the serratus anterior.
The lower medial quadrant is lying on the external oblique aponeurosis, which separates it from the rectus abdominis.
The breast tissue is separated from the pectoralis major muscle by the pectoral fascia. It's anchored anteriorly to the skin, posteriorly to the pectoral fascia by the cooper's ligament.
The outer prolongation of the gland into the axilla at the level of 3rd rib, is known as the axillary tail of spence. It enters the axilla by piercing the opening in the axillary fascia, known as the foramen of langer, and if it's enlarged, it can be mistaken as a lipoma.
The breast tissue is made up of acini, which forms the lobules, and the aggregations of these lobules made up the lobes. Each of these lobes are drained by a collecting duct, and 10-15 of these ducts drains out to the surface of nipple.
If there's a malignant breast lump, infiltrating the cooper's ligament, it'll lead to dimpling of the skin over breast, due to contraction of the cooper's ligament. If the tumour continues to infiltrate along these cooper's ligament, and now involving the pectoral muscle, it renders it lump non-mobile in a direction parallel to the direction of the pectoral muscle fibers, and mobile in a direction perpendicular to it.
If a tumour infiltrates into the major milk ducts, a subsequent fibrosis is going to cause the nipple to be drawn inwards, and hence leading to nipple retraction.
Peu'd orange, an appearance of orange skin of the skin of breast in infiltrative CA breast, is due to the tumour destruction of the cuticle lymphatics, leading to subsequent lymphostasis and edema, and hence the pits of hair follicles appears depressed from the surrounding skin.
Arterial supply
Lateral thoracic artery (major), a branch of the 2nd part of axillary artery
Perforating cutaneous branch of the interal mammary artery to the 2nd, 3rd, 4th space.
Lateral branches of the 2nd, 3rd, 4th intercostal arteries
Venous drainage
Intercostal veins, axillary veins and internal mammary veins
Lymphatic drainage
The primary lymphatic drainage of breast is the axillary nodes (around 20-30 of them), followed by the internal mammary nodes. Around 75% of the lymphatics of the breast is handled by the axillary nodes, and the remaining 25%, by the internal mammary nodes.
There are 5 groups of axillary nodes, namely the anterior, posterior, lateral, central and apical. By surgical means, they can be classified based on their position in relation with the pectoralis minor muscle.
Nodes located below the lateral border the pectoralis minor -> Level I (anterior, posterior and lateral)
Nodes located behind the pectoralis minor muscle -> Level II (central)
Nodes located above the medial border of pectoralis minor muscle -> Level III (apical)
Lymphatics from the lateral quadrant, some from the medial quadrant drains into the anterior nodes (located behind the lower border of pec. major muscle), and the posteior nodes, which then proceeds to the central nodes, and lastly the apical nodes.
Lymphatics from the right axillary and internal mammary nodes drains into the right subclavian lymphatic duct, whilst lymphatics from the left axillary and internal mammary nodes drains into the thoracic duct, then into the subclavian vein. Both eventually drains into the subclavian vein.
Common presenting problem of the breast
1) Painless lump
Breast cancer
Fibroadenoma
An area of fibroadenosis
Breast cyst
2) Painful lump
An area of fibroadenosis
Breast cyst
Periductal mastitis
Breast abscess
Advanced breast carcinoma
3) Only pain
Cyclical mastalgia
Non-cyclical mastalgia
Very rarely, CA breast
4) Nipple changes
Destruction
Depression (retraction, inversion)
Duplication
Discharge
Deviation
Displacement
Remember these 6 Ds
Different causes of nipple discharge :
Fresh red (blood) -> Duct papilloma
Pinkish (blood + serum) -> CA breast
Greenish/Blackish -> Breast cyst
Creamy, pale yellowish -> Duct ectasia
Whitish -> Lactation
Occasionally, paget's disease of the nipple can be confused with eczema of the breast. To differentiate it :
Paget's disease Eczema
Unilateral Bilateral
No vesicles With vesicles
Doesn't itch Itches
May be associated with lump No lump
Nipple may not be intact Nipple is always intact
Post-menopausal Post-lactational
How do you approach in a case of breast lump?
It's by the tripple assessment, which includes history and examination, imaging and Biopsy
1) History
About the lump : Onset, side, site, duration, progression, initial size, current size
Any pain associated with the lump, and proceed to the details of pain
Is there any skin changes? (dimpling, nodules, ulceration, peu'd orange)
Ask about the onset, duration and progression
Is there any nipple discharge?
Ask about the onset, duration, amount, colour, foul-smelling
Is there any recent nipple retraction?
Is there any lumps felt in the axilla?
Then, proceed to the history of risk factors :
Age of menarche (<11 years old)
Age of menopause (>55 years old)
Age of first child birth (if <30 years old, lesser risk)
Parity index (no. of children)
History of breast feeding and the duration (at least 6 months)
Family history of breast cancer (first degree relatives)
HRT/OCP intake (controversial)
Post-menopausal obesity
Diet - Fatty food predilection
Then, h/o of metastases :
Consitutional -> h/o of weight lost, lost of appetite
Respiratory -> Cough, hemoptysis, dyspnoea
CNS -> Headache, vomiting, diplopia, focal neurological deficits, seizures
Liver -> Jaundice
Musculoskeletal -> Bone pain, pathological fractures
2) Examination
a) Comparison of both breasts
Patient is sitting up, both arms are at her side.
Now observe, any discrepency of size and shape of both breasts?
Is there any differences in between the nipples of both sides?
Is there any visible mass?
Now, ask the patient to lift up both of her arms above head
Observe if there's any accentuation of dimpling or distortion of the breasts?
Observe if both breast are elevated equally (if one is higher than the other, it means that the lump probably has fixed to the pec.major muscle)
Now, ask the patient to bend forwards.
Does both breast moves forwards equally?
If one doesn't move as the patient bend forwards, possibly it has fixed to the chest wall (intercostal muscles or ribs)
Now, examine the affected breast.
On inspection, note :
Size and shape - normal?
Skin over breast - peu'd orange, ulcers, nodules, dimpling, dilated veins
Nipple - retraction, discharge
Visible mass - size, shape, surface
Any ulcers - describe it
On palpation, palpate all 4 quadrants of the breast, including the central area and the axillary tail of spence. Note if there's any lump under headings of :
Number of lumps
Site
Size
Surface
Consistency
Tenderness
Edges
Mobility and fixity
First as the patient's hands are placed over her hips, try moving the lump.
If it's not mobile even when the muscles are relaxed, it means that the lump has infiltrated into the chest wall (skin/intercostal muscles).
If it's infiltrated into the serratus anterior, it'll be the same as infiltration to the chest wall, and noted as stage T4 in TMN staging system.
To test whether it has infiltrated to serratus anterior, ask the patient to push against the wall using both hands, and if renders the lump non-mobile, it means infiltration to serratus anterior has taken place.
If the tumour has already infiltrated into the pectoralis major muscle, the lump is mobile in a direction perpendicular to the muscle fibers, but not in a direction parallel to it. This can be confirmed by asking the patient to press firmly using her hands against her hips, and if the lump now is completely immobile, it means infiltration into the pectoralis major muscle has taken place.
Now, try to feel for any lumps of SC nodes.
Examine the axilla, and note any enlarged nodes in it's numbers, consistency, tenderness, fixity.
Percuss the parasternal region for any dullness.
Repeat the same procedure for the opposite breast and axilla.
Now, examine the abdomen -> hepatomegaly, ascites, PR and PV done (metastatic deposits)
Examine the lungs -> Chest wall tenderness, pleural effusions
Check for any bony tenderness
3) Imaging
For women below age of 40 years old, the imaging of choice is ultrasonography
For women above age of 40 years old, imaging of choice is mammography
4) Biopsy
FNAC
TRU-cut/core-needle biopsy
Incisional biopsy
Excisional biopsy
Further test done :
1) Liver function test - elevation of ALP is suggestive of liver metastases
2) Liver ultrasound - liver metastases
3) Chest X ray - pleural effusions, cannon-ball secondaries, rib erosions
4) CT abdomen and Bone scan (optional - not done in MUAR)
TMN staging of CA breast
Tis - Carcinoma in situ
T0 - No evidence of the presence of primary tumour
Tx - Primary tumour cannot be accessed (may be after BCS/mastectomy)
T1 - Size of tumour is < 2cm, not fixed to muslces
T2 - Size of tumour is 2-5cm, fixed to the muscles
T3 - Size of tumour is >5cm
T4a - Involvement of the chest wall
T4b - Involvement of the skin over breast
T4c - Both T4a and T4b present
T4d - Inflammatory carcinoma
N0 - No evidence of nodal metastases clinically
N1 - Ipsilateral axillary nodes palpable, mobile
N2 - Ipsilateral axillary nodes palpable, immobile
N3a - Both infraclavicular and axillary nodes palpable
N3b - Both internal mammary and axillary nodes palpable
N3c - Both axillary and supraclavicular nodes palpable
M0 - No distant metastases
M1 - Distant metastases present
Hence, the stages are :
Stage I - T1 N0 M0
Stage IIA - T0 N1 M0, or T1 N1 M0, or T2 N0 M0
Stage IIB - T2 N1 M0, or T3 N0 M0
Stage IIIA - T0/T1/T2 N2 M0 or T3 N1/N2 M0
Stage IIIB - T4 N0/N1/N2 M0
Stage IIIC - Any T N3 M0
Stage IV - Any T Any N, M1
Tuesday, December 29, 2009
Thoracic Trauma
Introduction
Thoracic trauma accounts for about 25% of all cases of trauma.
Most of the thoracic injuries are life theratening, where the commonest cause of morbidity and mortality is hypoxia and haemorrhage.
However, ironically upto 80% of the cases can be managed conservatively.
The key to succesful management here is early physiological resuscitation and accurate diagnosis.
Investigations
An approach towards chest injuries is the same as any other injuries in primary and secondary survey, as noted by the Advanced Trauma Life Support Protocol (ATLS). History and examination will be important, and probably the most useful tool is a chest radiography.
In an unstable patient, chest radiography can be done first, provided that it didn't interfere with the process of resuscitation. An ultrasound can give useful information about the presence of hematoma together with a contusion or just contusion alone. Chest drain can be both diagnostic and therapeutic, where the benefits outweights the risks.
Some pitfalls during investigations :
a) Failed to identify tracheal shift
b) Failed to pass NG tube due to failure to recognise diagphramatic rupture
c) During hemothorax, must auscultate both anterior and posterior chest
d) Failed to resuscitate the patient first before investigations are done (both should be done hand in hand)
Nowadays, CT scan made an important role in the management of chest injuries.
Not only it can provide details about ribs and verterbral fractures, it can pick up contusions, hematomas, pneumothoraces easily. In penetrating injuries, eg gunshot wounds, CT can even trace the track of penetration through the thorax. Though aortogram is the 'gold standard' in diagnosing disruption of thoracic aorta, CT scan yields the similar results.
Immediately life threatening chest injuries :
a) Airway obstruction
The commonest cause of early preventable death in a case of thoracic injury is airway obstruction, which blood, clots, secretions, dentures, teeth or even tongue can be a source of obstruction. Rapid removal usually relieves the obstruction.
Examples of injuries potentially causing airway obstruction :
a) Expanding neck hematomas
b) Bilateral mandibular fractures
Both a and b causing pharyngeal deviation and tracheal compression
c) Laryngeal injury with thyroid/cricoid cartilage fracture, and other tracheal injuries
What need to be done immediately is endotracheal intubation, as early as possible.
Since most of these conditions are insidious and yet progressive, and delay will render increased difficulty in inserting the ET tube.
b) Tension pneumothorax
Tension pneumothorax occurs when "one-way" valve is created in such a way that air is collected within the pleural cavity, without any means of escape. The source of air leakage can be originating from the chest wall or lung parenchyma. This results in significant compression over the affected lung, obstruction of the great veins compromising the venous return, mediastinal shift and eventually, compression of the opposite lung.
Common causes includes, penetrating chest injuries, blunt chest trauma with parenchymal injury, iatrogenic causes includes a central subclavian venepuncture or mechanical positive pressure ventilation that has gone wrong.
The clinical presentation is dramatic, with a panicky patient, complaints of dyspnoea, and with distended neck veins. Clinical signs : Tracheal shift to the opposite side (late presentation), diminished lung expansion over affected side, hyperresonant note on percussion, absence breath sounds.
Tension pneumothorax is a clinical diagnosis, NEVER EVER proceed to radiological investigations first.
If clinical diagnosis is establish, one should use a large bore needle, puncture the anterior chest and the 2nd intercostal space, along the midclavicular line. This is followed by inserting a chest tube over the 5th intercostal space at the anterior axillary line.
c) Pericardial tamponade
In a case of patient with shock and distended vein, pericardial tamponade must be differentiated from tension pneumothorax. Pericardial tamponade is usually caused by penetrating chest injuries, and due to the non-distensible feature of the pericardial sac, even accumulation of small volume of blood is going to cause significant mechanical obstruction which renders cardiac pump failure.
The typical presentation will be : Features of hemorrhagic shock, Raised JVP and CVP, muffled heart sounds. Some pitfalls of these presentation must be remembered :
i) In case where there's active bleeding from a site distant to site of pathology, the neck veins are not distended.
ii) In case where the patient is having circulatory collapse, CVP will not be raised
To buy time for preparing the patient for definite operative management, which is left thoracotomy and sternotomy, a needle pericardiocentesis and resuscitation can be done. Needle pericardiocentesis is NOT a substitute for surgical management, and is done with ECG guidance (related with high incidence of iatrogenic myocardial injury)
d) Open pneumothorax
This means an opening chest wound is present, where the size of the defect is > 3cm.
Every breath that is inhaled, more air will be accumulated within the affected hemithorax.
This eventually causes significant hypoventilation, and eventually hypoxia.
The signs and symptoms are directly proportional to the size of the defect.
Initial management includes covering the chest wound is a sterile plastic occlusive dressing, which is only adhered at 3 sites, creating a flutter-wave valve, while suction is continued, where the tube is connected to an underwater seal drainage bottle.
Remember, no 'sucking' chest wound should be covered completely before a controlled drainage is established..
Definite management : pulmonary debridement and closure of the wound.
Some pit falls regarding this conditions :
For adults, a larger tube is required (>28 FG in size)
Some patients may require 2 chest drains
In case where patient's condition doesn't improve despite adequate drainage, try reducing the pressure within the seal drainage bottle to 5cm H20.
Early mobilisation and physiotherapy is required
e) Massive hemothorax
Defined by : initial blood collection by chest drain of > 1500 ml or in on-going hemorrhage, > 200-300 ml/h of blood collected over a period of 2-3 hours.
Massive hemothorax usually occurs due to blunt injuries, rupturing the intercostal and internal mammary vessels. Blood is hence collected within the affected hemithorax, causing significant respiratory distress. It's recognised by signs of haemorrhagic shock, flat neck veins, diminished expansion, dullness on percussion, absence of breath sounds.
Initial management of massive hemothorax includes chest drain, resuscitation and sometimes, intubation. Blood from the pleural cavity must be drained as rapid and as complete as possible, in order to prevent possibility of empyema and later, fibrothorax.
Pit falls regarding massive hemothorax :
1) One must examine both anterior and posterior chest when the patient is lying in a supine position, since there's a chance where the affected lung 'floats' within the BLOODY thoracic cavity.
If you only auscultate the anterior chest - it'll be normal
2) Even after draining out about 500ml of blood, dullness still persist and radio-opacity still present -> emergency thoracotomy
f) Flial chest
Flial chest is defined as a loss of bony continuity of a chest wall segment with the rest of thoracic cage, caused by a blunt trauma, which occurs when there's :
i) 3 or more rib fractures
ii) occurs in more than 2-3 places
Flial chest is a clinical diagnosis, not by chest radiography.
It's done by observing few respiratory cycles, where the flial segment will be drawn inwards during inspiration.
Causes of hypoxia in flial chest : voluntary splinting due to pain, pulmonary contusion, defect in the mechanical movement of the rib cage
Initial management : opiate analgesics, oxygen support. If a chest drain is present, intrapleural local analgesia can be given. Ventilation is reseved for patients with respiratory failure despite optimal treatment given. Surgical fixation is done in severe thoracic injury or in cases where pulmonary contusion is present.
Saturday, December 26, 2009
A case of Acute testicular pain
History

We have a 16 years old male here presented to the ER complaining of sudden onset of right testicular pain. The pain woke him up from his sleep and has persisted over the last 3 hrs. His mother says that he has vomited once. His previous medical history includes a similar event a year ago, but on that occasion the pain subsided quickly. He is an asthmatic and uses a salbutamol inhaler.
Only with h/o, what's your differential diagnosis?
Testicular torsion?
Acute epididymo-orchitis?
Torsion of appendix testis?
Infected hydrocele?
Strangulated hernia?
Testicular rupture?
Haemorrhage into a tumour?
On examination
The left hemi-scrotum feels normal but the right side is acutely swollen and tender on palpation. The testicle is elevated when compared to the other side and has an abnormal horizontal lie. The abdomen is soft, non tender, with intact hernial orifices. Vitals are stable, cremesteric reflex is absent.
So, what's your provisional diagnosis?
In this case, testicular torsion should be ruled out unless proven otherwise. Points towards diagnosis of testicular torsion :
1) Age (testicular torsion is common in age group of 10-25 yrs old)
2) Elevated, tender right testicle
3) Abnormal horizontal lie (risk factor for torsion)
4) Cremesteric reflex is absent (bear in mind that presence of this reflex doesn't rule out testicular torsion!)
If doppler's ultrasound is immediately available, a results showing interrupted blood supply to the testis is diagnostic.
However, if the diagnosis is in doubt, PLS peform surgical exploration to confirm the diagnosis. If not, he CAN SUE YOU BECOZ you've caused him to lose his precious balls.

Remember, you've only 4-6 hours (starting from the time of onset of pain) to salvage the balls.
However, if the patient presented within the first hour after onset of pain, it's sometimes possible to untwist the cord manually, which if succesful, the affected testicle is out of danger and surgery can be planned later.
And, surgical correction is bilateral, since congenital defects often involves both sides.
Tuesday, December 15, 2009
Head injury - part 3
Management of mild head injury (GCS 14-15)
Most of the occasions, patients with mild head injury, after history and examination, and a period of observation, will be allowed to be discharge after following criterias met :

Battle's sign
a) Full GCS score (15/15)
b) No focal neurological deficits
c) Accompanied by a responsible adult
d) Not under influence of any drugs/alcohol
e) Verbal/Written advice about the injury given

Statement e) means : Advice regarding any worsening of symptoms, such as persistent headahce not relieved by analgesia, severe vomiting, blurring of vision, diplopia, weakness/numbness of limbs have been given verbally or written.
Sometimes, for patients with mild head injury, decision of whether to perform CT brain or not can be a big headahce. However, here are the NICE guidelines regarding indications of CT brain in patients with mild head injury :
a) GCS is <13 at any point
b) GCS is 13-14 at 2 hours time
c) Evidence of focal neurological deficit
d) Suspicion of open, comminuted, depressed, or basal skull fracture
e) Vomiting > 1 episode
f) Seizures
Urgent indication
a) Age > 65 years old
b) Evidence of coagulopathy (liver disease, blood dyscarias, warfarin, anti-platelet medications)
c) Dangerous mechanism of head injury (CT within 8 hrs)
d) Antegrade amnesia > 30 mins (CT within 8 hrs)
Management of moderate/severe head injury
First of all, resuscitation and primary survery.
After stabilising cervical spine at 3 fixation point, start primary surveying.
Remember that normalising the patient's oxygenation and circulation is more important than getting a CT done! This is to prevent secondary brain injury
After primary survey, you've made a diagnosis of moderate/severe head injury, the next step is CT brain, to detect any intracranial hematoma, or any skull fractures, soft tissue injuries, or any mild intracerebral contusion.
For intubated patients, it's recommended that you've asked for CT cervical spine.
Before ariving at the hospital, some conservative management can be given for raised ICP, which includes :
a) Reversed tredelenburg : Raised head upto 20-30 degrees
b) Check if the cervical collar is too tight (may obstruct venous drainage from brain)
c) If there's pupillary dilatation (may be due to acute raised ICP), 0.5mg/kg 20% IV mannitol can be given.
Medical management of severe head injury
Severe head injury is preferably managed in a neurointensive care unit.
ICP can be monitored by passing a catheter into the frontal horn of the lateral ventricle (2 finger breadth from the blurred hole, behind the hairline)
Raise the patient's head for about 20-30 degrees
Protect the patient's airway!
For those with traumatic brain injury and coma, they are more prone to aspiration.
Preferably intubate the patient, and provide high flow oxygen. (Prevent hypoxia)
Make sure that the cervical collar is not too tight.
Cerebral vasculatures are very sensitive to the PCo2 level. When there's a rise in PCo2 level, the cerebral vasculatures dilates, and elevates the ICP. In contrast, when there's a fall in PCo2 level, cerebral vasculature constricts.
Hence, you must try to maintain the PCo2 level in between 4.5-5kPa.
Some experienced anesthetist may induce hyperventilation in patients to cause temporary reduction in ICP by reducing the PCo2 level.
Sedative given, either with or without muscle relaxant.
Mannitol/Frusemide given to reduce cerebral edema.
Patient is prone for hyponatremia or other electrolyte imbalance -> correct it
Avoid pyrexia, as it'll cause undesirable increase in the brain metabolic activity.
Barbiturates eg: thiopentone sodium is given to reduce ICP and brain metabolic rate.
Prophylactic anticonvulsant given.
Most of the occasions, patients with mild head injury, after history and examination, and a period of observation, will be allowed to be discharge after following criterias met :

a) Full GCS score (15/15)
b) No focal neurological deficits
c) Accompanied by a responsible adult
d) Not under influence of any drugs/alcohol
e) Verbal/Written advice about the injury given

Racoon's Sign
Statement e) means : Advice regarding any worsening of symptoms, such as persistent headahce not relieved by analgesia, severe vomiting, blurring of vision, diplopia, weakness/numbness of limbs have been given verbally or written.
Sometimes, for patients with mild head injury, decision of whether to perform CT brain or not can be a big headahce. However, here are the NICE guidelines regarding indications of CT brain in patients with mild head injury :
a) GCS is <13 at any point
b) GCS is 13-14 at 2 hours time
c) Evidence of focal neurological deficit
d) Suspicion of open, comminuted, depressed, or basal skull fracture
e) Vomiting > 1 episode
f) Seizures
Urgent indication
a) Age > 65 years old
b) Evidence of coagulopathy (liver disease, blood dyscarias, warfarin, anti-platelet medications)
c) Dangerous mechanism of head injury (CT within 8 hrs)
d) Antegrade amnesia > 30 mins (CT within 8 hrs)
Management of moderate/severe head injury
First of all, resuscitation and primary survery.
After stabilising cervical spine at 3 fixation point, start primary surveying.
Remember that normalising the patient's oxygenation and circulation is more important than getting a CT done! This is to prevent secondary brain injury
After primary survey, you've made a diagnosis of moderate/severe head injury, the next step is CT brain, to detect any intracranial hematoma, or any skull fractures, soft tissue injuries, or any mild intracerebral contusion.
For intubated patients, it's recommended that you've asked for CT cervical spine.
Before ariving at the hospital, some conservative management can be given for raised ICP, which includes :
a) Reversed tredelenburg : Raised head upto 20-30 degrees
b) Check if the cervical collar is too tight (may obstruct venous drainage from brain)
c) If there's pupillary dilatation (may be due to acute raised ICP), 0.5mg/kg 20% IV mannitol can be given.
Medical management of severe head injury
Severe head injury is preferably managed in a neurointensive care unit.
ICP can be monitored by passing a catheter into the frontal horn of the lateral ventricle (2 finger breadth from the blurred hole, behind the hairline)
Raise the patient's head for about 20-30 degrees
Protect the patient's airway!
For those with traumatic brain injury and coma, they are more prone to aspiration.
Preferably intubate the patient, and provide high flow oxygen. (Prevent hypoxia)
Make sure that the cervical collar is not too tight.
Cerebral vasculatures are very sensitive to the PCo2 level. When there's a rise in PCo2 level, the cerebral vasculatures dilates, and elevates the ICP. In contrast, when there's a fall in PCo2 level, cerebral vasculature constricts.
Hence, you must try to maintain the PCo2 level in between 4.5-5kPa.
Some experienced anesthetist may induce hyperventilation in patients to cause temporary reduction in ICP by reducing the PCo2 level.
Sedative given, either with or without muscle relaxant.
Mannitol/Frusemide given to reduce cerebral edema.
Patient is prone for hyponatremia or other electrolyte imbalance -> correct it
Avoid pyrexia, as it'll cause undesirable increase in the brain metabolic activity.
Barbiturates eg: thiopentone sodium is given to reduce ICP and brain metabolic rate.
Prophylactic anticonvulsant given.
Head Injury - part 2
Extradural hematoma

This refers to collection of blood in between the skull and dura mater.
More commonly seen in younger patients (children, adolescence)
Extradural hematoma is always associated with skull fractures, most frequently, the temporal bone. (since pterion is the thinnest part of skull, involvement of this area causes tearing of the middle meningeal artery)
Of course, involvement of the posterior fossa and frontal bone is also possible.
However, the hematoma is not always arterial in origin, it may be due to a tear to the dural venous sinuses as well.
Classical presentation of extradural hematoma is : (<1/3 of the cases)
Lucid interval, where after initial injury, patient is conscious, alert, oriented, and only complaints of headache. Minutes or hours later, the condition worsens, with deterioration of consciousness, contralateral hemiparesis/plegia, and ipsilateral pupillary dilatation.

Early diagnosis and treatment of subdural hematoma is VITAL.
CT brain is confirmatory, where it'll appears as a lentiform, biconvex, or lense-shaped hyperdense mass in between the skull and brain, with or without midline shift.
After diagnosis is confirmed, surgical evacuation of the hematoma is required, where craniotomy is performed.
Acute subdural hematoma (ASH)

This is actually more common, with poorer prognosis, higher mortality rate as compared to extradural hematoma.
It refers to blood collection in between the dura and arachnoid mater.
ASH is almost always associated with a primary brain injury.
Most of the time at presentation, the patient has impaired consciousness, which rapidly deteriorates depending on the size of the hematoma.

Again, CT brain is diagnostic.
It'll appears as a crescent shaped, more diffuse (with concavity towards the brain), hyperdense mass in between the brain and skull.
Treatment - surgical evacuation by craniotomy
Chronic subdural hematoma (CSH)
CSH often seen in elderly patients, who is on anti-platelets or anti-coagulants. It is believed to be due to tearing of the bridging veins, which causes formation of clinically inapparent, small ASH. Later, as it breaks down and the volume expands, it becomes symptommatic.
Mostly, patients presents with headache, focal neurological deficit, impaired cognition, seizures, etc (hence, one of the d/d of CVA)
CT brain intepretation :
Acute blood (0-10 days) = hyperdense
Subacute blood (10 days - 2 weeks) = isodense
Chronic blood (>2weeks) = hypodense
Treatment = creating a blurr hole and evacuate the hematoma
This refers to collection of blood in between the skull and dura mater.
More commonly seen in younger patients (children, adolescence)
Extradural hematoma is always associated with skull fractures, most frequently, the temporal bone. (since pterion is the thinnest part of skull, involvement of this area causes tearing of the middle meningeal artery)
Of course, involvement of the posterior fossa and frontal bone is also possible.
However, the hematoma is not always arterial in origin, it may be due to a tear to the dural venous sinuses as well.
Classical presentation of extradural hematoma is : (<1/3 of the cases)
Lucid interval, where after initial injury, patient is conscious, alert, oriented, and only complaints of headache. Minutes or hours later, the condition worsens, with deterioration of consciousness, contralateral hemiparesis/plegia, and ipsilateral pupillary dilatation.

Early diagnosis and treatment of subdural hematoma is VITAL.
CT brain is confirmatory, where it'll appears as a lentiform, biconvex, or lense-shaped hyperdense mass in between the skull and brain, with or without midline shift.
After diagnosis is confirmed, surgical evacuation of the hematoma is required, where craniotomy is performed.
Acute subdural hematoma (ASH)

This is actually more common, with poorer prognosis, higher mortality rate as compared to extradural hematoma.
It refers to blood collection in between the dura and arachnoid mater.
ASH is almost always associated with a primary brain injury.
Most of the time at presentation, the patient has impaired consciousness, which rapidly deteriorates depending on the size of the hematoma.

Again, CT brain is diagnostic.
It'll appears as a crescent shaped, more diffuse (with concavity towards the brain), hyperdense mass in between the brain and skull.
Treatment - surgical evacuation by craniotomy
Chronic subdural hematoma (CSH)
CSH often seen in elderly patients, who is on anti-platelets or anti-coagulants. It is believed to be due to tearing of the bridging veins, which causes formation of clinically inapparent, small ASH. Later, as it breaks down and the volume expands, it becomes symptommatic.
Mostly, patients presents with headache, focal neurological deficit, impaired cognition, seizures, etc (hence, one of the d/d of CVA)
CT brain intepretation :
Acute blood (0-10 days) = hyperdense
Subacute blood (10 days - 2 weeks) = isodense
Chronic blood (>2weeks) = hypodense
Treatment = creating a blurr hole and evacuate the hematoma
Monday, December 14, 2009
Head injury - part 1
Pathophysiology
90% of the brain metabolism requires blood-borned glucose.
During normal circumstances, the cerebral autoregulation mechanism maintains the cerebral blood flow above 70mmHg, even though the Mean Arterial Pressure (MAP), varies as much as between 50mmHg - 150 mmHg.
*Cerebral perfusion pressure (CPP) = MAP - ICP
However, when there's head injury, this autoregulatory mechanism is disordered. Hence, the CPP fluctuates with MAP, and hence, brain is more vulnerable towards ischaemia.
According to Monro-Kellie's hypothesis, our skull is a rigid structure, and hence will not expand. Intracranial pressure is directly proportionate to the increase in volume of the intracranial structures, including vascular components (blood in vessels), Cerebrospinal fluid (CSF), or the brain tissue itself.
Initially, when there's formation of a space-occupying lesion, the rise in ICP is prevented by transient displacement of venous blood and CSF away from the brain. This decrease in volume compensates for the rise in volume due to formation of space occupying lesion.
But, further rise in the volume of a brain compartment -> even a slightest increase in volume is going to cause a surge in ICP.
Note : ICP can be measured by passing a catheter through the frontal horn of lateral ventricle. In head injuries, ICP is monitored in btw 5-15 mmHg. Bear in mind that normal ICP is <10mmHg
One should never forget that intracranial hypertension is the dreadliest consequence of head injury. The end-stage of raised ICP will be cerebral herniation, which can be :
a) Herniation through the Tentorial hiatus
Tentorial hiatus is an opening at the tentorium cerebelli
As with central herniation, involving the midbrain, features are :
-> Altered consciousness due to midbrain ischaemia
-> Increased muscle tone, and eventually decorticate rigidity
-> Bilateral +ve babinski's sign
-> pupillary constriction, which followed by dilatation, and lastly, becomes static
As for Lateral herniation, involving the temporal lobe (uncus) :
-> Altered consciousness
-> Contralateral hemiparesis, hemiplegia
-> Compression on the 3rd nerve, initially causing ipsilateral pupillary constriction, followed by dilatation, then becomes fixed to light response. Continued rise in ICP results in involvement of the contralateral side of pupil. The sequence of changes in pupillary response is known as Hutchingson's pupil.
-> Others : ptosis, eye deviated inferolaterally
b) Herniation into foramen magnum
If ICP continues to rise, the cerebellar tonsils will herniates into the foramen of magnum, thereby compressing the brainstem and medulla.
This results in Cardiorespiratory collapse, bilateral pinpoint pupil, and flaccid quadriplegia due to lateral corticospinal tract compression.
Note : Signs of Raised intracranial pressure
Papilloedema (swollen optic disc)
Altered level of consciousness
Bradycardia*
Widened pulse pressure*
Decreased systolic BP*
Abnormal breathing pattern (Cheyne's-Stokes/Hyperventilation)
*Cushing's triad
DO NOT PERFORM LUMBAR PUNCTURE IN A PATIENT WITH RAISED ICP!!
Classification of Head injuries
Classification can be made via :
a) Glasgow Coma scale
Minor head injury = No lost of consciousness and GCS is full 15/15
Mild head injury = GCS 14-15 with lost of consciousness
Moderate head injury = GCS 9-13
Severe head injury = GCS 3-8
b) Mechanism of head injury
i) Blunt trauma
Direct injury (Croup injury)
The brain substance collide against a fixed skull.
Usually caused by sudden deceleration/acceleration forces
Resulting in contusion, laceration and intra-cranial bleeding
Indirect injury (Counter-croup)
Injury to the side opposite to the side of trauma.
Hence, subdural/extradural hematoma may be seen opposite to the side blunt trauma
Rotational injury
This occurs in acceleration/deceleration injury.
Such forces creates rotational injury at the junction btw white/grey matter of brain.
ii) Penetrating injury
High velocity - gunshot injuries
Low velocity - stab injuries
In penetrating injury, there's risk of intracranial infection, due to introduction of foreign bodies
c) Morphological
i) Scalp injuries
Cephalhematoma
More commonly seen in infants and children.
Due to collection of blood under the periosteum, resulting in formation of a tense swelling, confined to the margins of underlying bones.
It takes weeks to resolve
Subaponeurotic hematoma
Blood collection in between aponeurosis and pericranium
Formation of a fluctuant swelling involving the whole scalp
Take weeks to resolve as well
Others : Scalp laceration, Scalding (avulsion)
ii) Skull fractures
It can involve the vault or base, and can be open or closed.
In closed fractures, there's no communication with the exterior, so do not expect a nose, ear bleed or leakage of CSF.
For open vault fractures, expect visible brain substance.
For open base fractures :
If it's an anterior cranial fossa fracture -> Raccoon's Sign (periorbital hematoma) + subconjunctival haemorrhage with no posterior limits + CSF rhinnorhoea and nose bleeding
If it's a middle cranial fossa fracture -> Battle's sign (Bruises seen over mastoid and post-auricular region, which forms within 48 hrs) CSF otorrhoea and ear bleeding
Posterior cranial fossa fracture is not easily identified clinically. Most of the time, when there's occipital bone fracture, there'll be a dural venous sinus tear. Usually, there'll be hypertension, bradycardia, changes in respiration and consciousness.
A closed fracutre can be depressed, communited, or linear.
d) Primary/Secondary
Primary head injury occurs during time of impact, it's irreversible, and not treatable, and recovery will largely depends on the type and extent of injury. Remember that neurons once damaged, will not regenerate.
Hence, most of the our treatment will be focusing on secondary head injury.
Causes of Secondary head injury :
1) Hypoxia, with PaO2 <8Kpa
2) Hypotension, with SBP <90mmHg
3) Cerebral perfusion pressure <65mmHg
4) Intracranial pressure >20 mmHg
5) Pyrexia
6) Seizures
7) Metabolic disturbances
e) Intracranial hematomas
Extradural hematoma
More common in children as their dura strips easily to accomodate blood clot
Here, blood collects between the skull and dura mater
Common at the frontal and temporal region, usually associated with local fractures
Middle meningeal artery or dural venous sinuses are teared
Classical presentation : Lucid interval
Others : Headache, vomiting, lost of consciousness, hemiparesis, seizures, signs of raised ICP
Diagnosis is confirmed by CT brain, which reveals a biconvex, lense-shaped hyperdense hematoma.
If the hematoma is stable, conservative treatment suffice.
However, if there's evidence that it's enlarging, perform blurr hole and craniotomy
Subdural hematoma
More common than extradural hematoma
Here, blood collects between the dura mater and arachnoid mater
Clinical features are similar to extradural hematoma
CT brain reveals a cresent shaped hematoma, which concavity directing towards the brain.
Treatment - same
HISTORY TAKING IN HEAD INJURY
1) How did you injure your head?
Basically, you're asking what's the mechanism of injury.
For dangerous mechanisms, such as falling from a height, or high-speed motor vehicle accident, it may be a multisystem injury, including the spine.
For head injury with lost of consciousness, but without any accidental mechanism, consider hypoglycemia, syncope, aneurysmal subarachnoid haemorrhage
2) Ask about the neurological state of patient during and after injury
Is there lost of consciousness?
Is there seizures?
Is the patient able to respond, move, or talk properly after the injury?
Is there antegrade (can't recall what happened after injury) or retrograde (can't recall what happened before injury) amnesia?
3) Then, What's the GCS of the patient during the scene, prior to intubation, and on arrival in hospital?
4) Is there any evidence suggestive of hypoxia, or any cardiovascular instability?
5) Any co-morbid medical illness?
6) Is the patient taking any drugs? (esp antiplatelets or anticoagulants)
7) Any ilicit drung intake or alcohol consumption
TO BE CONTINUED.....
Sunday, December 13, 2009
Testicular Tumour
Just breifly describe about this uncommon, but important condition
First, we'll talk about the anatomy :

Testes are originally retroperitoneal organs, during intra-uterine life.
Just before guys are born, our balls descends down, through the inguinal canal, and enters the scrotal sac at the perineum.
As it descends, it bring along vessels, nerves, lymphatics, and it's primary drainage duct - the vas deferens
All these structures are kept safely within the spermatic cord, which can be described of having :

3 vessels : Cremesteric artery, Artery to Vas, and Testicular artery
3 nerves : Autonomic nerves, Genital branch of genitofemoral nerve, and illioinguinal nerve
3 structures : Lymphatics, Pampiniform venous plexus, and Vas deferens
3 coverings : Cremesteric fascia, Internal and external spermatic fascia
The anterior aspect of our testis is covered by a closed peritoneal sac, known as the tunica vaginalis, formed as a result of the obliteration of processus vaginalis.
The posterolateral aspect, is where a single, long coiled duct located, which is the epididymis.
2 histopathological types of Testicular tumour :
1) Seminoma - arising from the seminiferous tubules
2) Teratoma - it's a malignant germ cell tumour
History taking
1) Age
For teratoma, it's common among young men, around 20-30 yrs of age.
Seminoma may be more common in individuals around 30-40 yrs of age.
2) Symptoms
Now, the usual scenario is : the only symptom is a scrotal swelling
Since this condition is usually painless.
Occasionally, there might be some amount of dragging, or dull-aching pain.
Especially when the swelling increases in it's size, the patient might complaints of heaviness over the affected testicles.

In advanced malignancy, there might be symptoms suggesting of metastasis, eg : breathlessness, lost of appetite/weight, abdominal pain, etc
Examination
1) Inspection
A scrotal swelling is seen, not extending into the inguinal region
No expansile cough impulse seen
Scrotal skin - stretched but with normal rugosity, but in advanced stage, skin may ulcerate/infected
No lumps, no scars, no sinuses
2) Palpation
Able to get above the swelling (pure scrotal swelling la)
Testis is enlarged, swollen
Hard in consistency, non tender
There's loss of testicular sensation, and it's feels heavier than the normal side
Spermatic cord is normal
Skin may not be pinchable if infiltration had taken place
Non-fluctuant, non-transilluminant
3) Please examine the para-aortic and supraclavicular lymph nodes
4) Examine the abdomen -> any hepatomegaly? any masses?
Auscultate the lungs -> any signs of metastases?
Investigation
Here I'll try not to be lengthy la har....
1) Blood : Alpha-fetoprotein, B-HCG, and LDH (Tumour markers)
2) Chest X ray (cannon-ball metastases)
3) CT abdomen for staging
4) Orchidectomy and sent specimen for histological analysis
How do we stage it?
Stage I : Only involve the testis
Stage II : Involving the nodes below diagphram
Stage III : Involving the nodes above diagphram
Stage IV : Hepatic/Pulmonary metastasis


So, see how scary it is...
LOVE UR BALLS, MAN!!
First, we'll talk about the anatomy :

Testes are originally retroperitoneal organs, during intra-uterine life.
Just before guys are born, our balls descends down, through the inguinal canal, and enters the scrotal sac at the perineum.
As it descends, it bring along vessels, nerves, lymphatics, and it's primary drainage duct - the vas deferens
All these structures are kept safely within the spermatic cord, which can be described of having :

3 vessels : Cremesteric artery, Artery to Vas, and Testicular artery
3 nerves : Autonomic nerves, Genital branch of genitofemoral nerve, and illioinguinal nerve
3 structures : Lymphatics, Pampiniform venous plexus, and Vas deferens
3 coverings : Cremesteric fascia, Internal and external spermatic fascia
The anterior aspect of our testis is covered by a closed peritoneal sac, known as the tunica vaginalis, formed as a result of the obliteration of processus vaginalis.
The posterolateral aspect, is where a single, long coiled duct located, which is the epididymis.
2 histopathological types of Testicular tumour :
1) Seminoma - arising from the seminiferous tubules
2) Teratoma - it's a malignant germ cell tumour
History taking
1) Age
For teratoma, it's common among young men, around 20-30 yrs of age.
Seminoma may be more common in individuals around 30-40 yrs of age.
2) Symptoms
Now, the usual scenario is : the only symptom is a scrotal swelling
Since this condition is usually painless.
Occasionally, there might be some amount of dragging, or dull-aching pain.
Especially when the swelling increases in it's size, the patient might complaints of heaviness over the affected testicles.

No, It's not painful...
In advanced malignancy, there might be symptoms suggesting of metastasis, eg : breathlessness, lost of appetite/weight, abdominal pain, etc
Examination
1) Inspection
A scrotal swelling is seen, not extending into the inguinal region
No expansile cough impulse seen
Scrotal skin - stretched but with normal rugosity, but in advanced stage, skin may ulcerate/infected
No lumps, no scars, no sinuses
2) Palpation
Able to get above the swelling (pure scrotal swelling la)
Testis is enlarged, swollen
Hard in consistency, non tender
There's loss of testicular sensation, and it's feels heavier than the normal side
Spermatic cord is normal
Skin may not be pinchable if infiltration had taken place
Non-fluctuant, non-transilluminant
3) Please examine the para-aortic and supraclavicular lymph nodes
4) Examine the abdomen -> any hepatomegaly? any masses?
Auscultate the lungs -> any signs of metastases?
Investigation
Here I'll try not to be lengthy la har....
1) Blood : Alpha-fetoprotein, B-HCG, and LDH (Tumour markers)
2) Chest X ray (cannon-ball metastases)
3) CT abdomen for staging
4) Orchidectomy and sent specimen for histological analysis
How do we stage it?
Stage I : Only involve the testis
Stage II : Involving the nodes below diagphram
Stage III : Involving the nodes above diagphram
Stage IV : Hepatic/Pulmonary metastasis


So, see how scary it is...
LOVE UR BALLS, MAN!!
Subscribe to:
Posts (Atom)